
Collagen Supplements: Evidence, Forms and What Works

What collagen supplements do, which forms are studied, and what dosing trials have tested. Evidence from systematic reviews and clinical data.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
Collagen supplements are hydrolyzed peptides taken orally to support skin elasticity, joint function, and connective tissue structure. Clinical trials have tested daily doses ranging from 2.5 to 15 grams, primarily using type I and type II hydrolysates. Evidence from systematic reviews shows measurable effects on skin hydration and joint pain in some populations, but individual response varies and long-term data remain limited.
What Collagen Supplements Contain
Most products contain hydrolyzed collagen peptides derived from bovine, marine, or chicken sources. The hydrolysis process breaks intact collagen into smaller peptides, typically 2,000 to 5,000 Daltons, which are absorbed in the intestine.
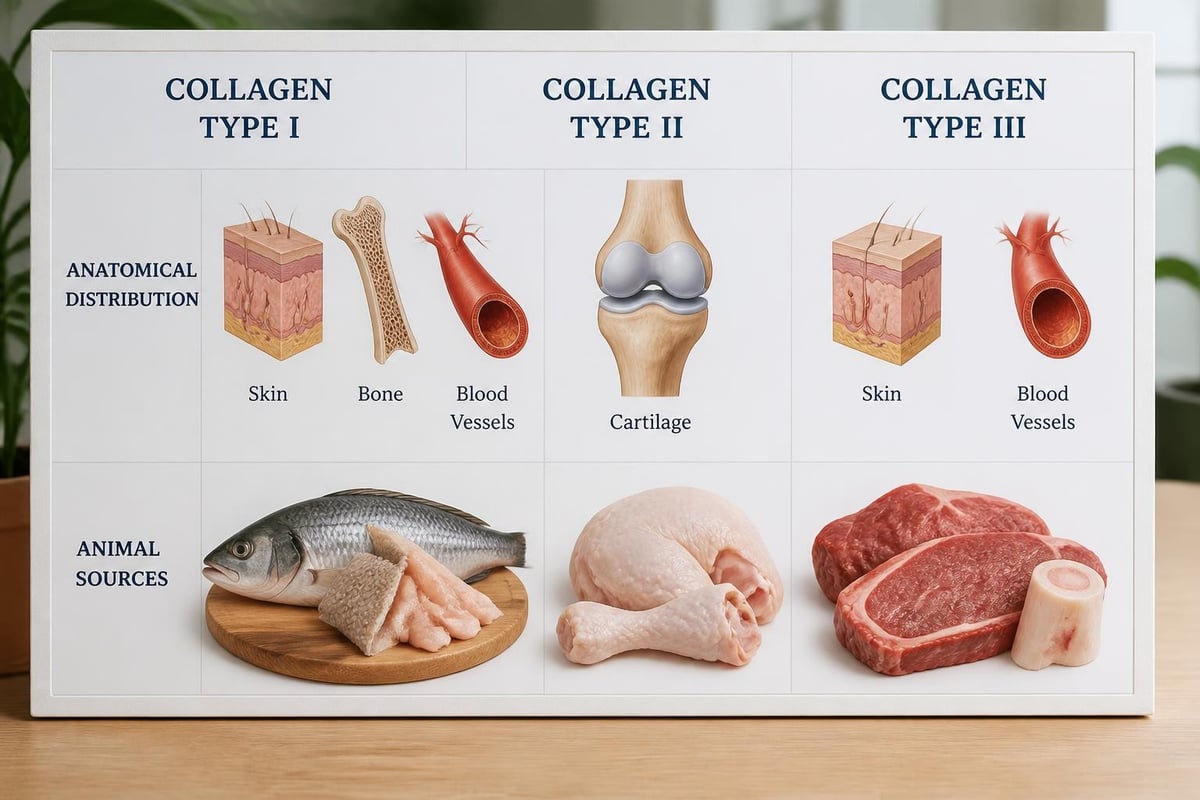
Type I collagen makes up approximately 90% of the body's collagen and is found in skin, tendons, and bone. Bovine and marine supplements typically provide type I.
Type II collagen is concentrated in cartilage. Chicken sternum is the common source for type II hydrolysates used in joint-focused formulations.
Type III collagen appears alongside type I in skin and blood vessels. Some multi-source blends include type III, though trial data focus on types I and II.
Peptide size matters for absorption. Research on collagen structure shows that smaller peptides reach the bloodstream intact, whereas larger fragments undergo further digestion. Labels rarely specify peptide weight distribution, so source and hydrolysis method serve as proxies for quality.
Forms and Delivery
Collagen supplements appear as powders, capsules, liquids, and functional foods. Bioavailability does not differ significantly among these forms when peptide size is controlled. Powder allows flexible dosing. Capsules standardize intake but require multiple units to reach trial-tested doses. Liquids often add sugars or preservatives.
Combination products include vitamin C, hyaluronic acid, or ceramides. Vitamin C is required for endogenous collagen synthesis, so co-supplementation has a mechanistic rationale, though trials have not consistently separated the effect of collagen from that of co-factors.
Evidence for Skin Outcomes
A 2025 umbrella review summarized 19 systematic reviews covering skin hydration, elasticity, and wrinkle depth. The majority of included trials used 2.5 to 10 grams per day of type I collagen peptides for 8 to 12 weeks.
Skin hydration improved in several randomized controlled trials, with effect sizes ranging from small to moderate. One meta-analysis reported a weighted mean increase of approximately 7% in dermal hydration measured by corneometry.
Elasticity showed smaller but statistically significant gains in some studies. Measurement methods varied, including cutometry and visual grading scales, making direct comparison difficult.
Wrinkle depth reductions were observed in a subset of trials, but placebo effects and concurrent use of topical treatments complicate interpretation.
| Outcome | Typical Dose (g/day) | Duration (weeks) | Effect Size |
|---|---|---|---|
| Skin hydration | 2.5–10 | 8–12 | Small to moderate |
| Elasticity | 5–10 | 8–12 | Small |
| Wrinkle depth | 5–10 | 12 | Inconsistent |
The mechanisms are debated. Peptides may stimulate fibroblast activity or provide amino acids for new collagen synthesis. Alternatively, they may reduce matrix degradation. The evidence does not yet distinguish among these pathways.
Joint and Musculoskeletal Effects
Systematic reviews on knee osteoarthritis have tested type II collagen at doses of 40 mg (undenatured) and 10 grams (hydrolyzed) per day. Both forms reduced pain scores on the WOMAC and VAS scales after 12 to 24 weeks.
Pain reduction was modest but clinically relevant in individuals with mild to moderate arthritis. Effect sizes were larger in trials using hydrolyzed collagen at higher doses.
Functional improvement appeared in mobility tests, including timed-up-and-go and stair-climbing speed, though the magnitude varied across studies.
Cartilage biomarkers (such as CTX-II) decreased in some trials, suggesting reduced cartilage degradation, but imaging studies have not consistently shown structural changes in joint space or cartilage thickness.
A 2024 review of type I hydrolysate examined bone and muscle outcomes. Bone mineral density showed no significant change in most trials. Lean mass increased slightly in older adults when collagen was combined with resistance training, but the isolated effect of supplementation was unclear.
Athletes have used collagen peptides to reduce exercise-related joint pain. Trial durations were short (4 to 12 weeks), and the populations were small, so conclusions remain tentative.

Dosing and Duration in Published Trials
Most human trials have used between 5 and 10 grams per day. Lower doses (2.5 grams) appeared in skin-focused studies. Higher doses (15 grams) were tested for joint pain but did not consistently outperform 10 grams.
Duration matters. Trials shorter than 8 weeks rarely showed significant effects. Skin outcomes emerged by 8 to 12 weeks. Joint pain required 12 to 24 weeks for measurable improvement.
Timing has not been rigorously tested. Some protocols recommend taking collagen on an empty stomach to optimize absorption. Others suggest pairing it with vitamin C. No head-to-head trial has compared these approaches.
Body weight was not a dosing variable in most studies, though pharmacokinetic modeling suggests heavier individuals may require higher doses to achieve equivalent serum peptide levels.
Harvard Health notes that the majority of trials were funded by manufacturers, raising questions about publication bias. Independent replication is limited.
Safety and Regulatory Context
Collagen peptides are classified as food or dietary supplements in most jurisdictions. They are not subject to the pre-market approval required for pharmaceuticals. Safety evaluations focus on allergenicity, contamination, and manufacturing standards.
Allergens include bovine and marine proteins. Individuals with fish or shellfish allergies should verify marine collagen sources. Chicken-derived type II products may contain trace egg or soy proteins depending on processing.
Contaminants such as heavy metals have been detected in some marine collagen products. Third-party testing for lead, cadmium, and mercury is advisable but not mandatory in all markets.
The European Food Safety Authority has reviewed collagen and gelatine safety, focusing on transmissible spongiform encephalopathy (TSE) risk from ruminant sources. Processing methods that include acid or enzymatic hydrolysis reduce but do not eliminate this risk.
In the United States, the NIH Dietary Supplement Label Database catalogs product labels and claims. Variability in ingredient disclosure is common. Some labels list "collagen peptides" without specifying type, source, or molecular weight.
Adverse events are rare. Gastrointestinal discomfort, including bloating and mild nausea, has been reported at doses above 10 grams per day. No serious safety signals have emerged in published trials.
Measuring Response
Collagen supplementation does not produce immediate, visible changes. Measuring outcomes requires either laboratory testing or validated scales.
Skin assessment uses corneometry for hydration, cutometry for elasticity, and photography with image analysis for wrinkle depth. Subjective scales, such as the Global Aesthetic Improvement Scale, are common but vulnerable to bias.
Joint function is measured using the WOMAC index (pain, stiffness, function), the visual analog scale for pain, and timed physical performance tests. Imaging (MRI or ultrasound) can assess cartilage thickness and synovial inflammation, though changes are subtle and require high-resolution protocols.
Biomarkers include procollagen peptides (markers of collagen synthesis) and collagen degradation fragments (CTX-I for bone, CTX-II for cartilage). These are available through specialized laboratory panels. Advanced diagnostic testing that includes matrix turnover markers can track response over time, though no standardized collagen-specific panel exists.
Without objective measurement, anecdotal reports of benefit are difficult to interpret. Placebo response rates in skin and joint trials are consistently high.

Limitations in Current Evidence
Most trials enrolled healthy middle-aged adults or individuals with mild arthritis. Data in older populations, athletes under heavy training loads, and those with significant skin damage remain sparse.
Study quality varies. Many trials had small sample sizes (n = 30 to 60), short durations, and industry funding. Blinding was adequate in most randomized controlled trials, but conflicts of interest were common.
Mechanistic understanding is incomplete. It is unclear whether absorbed peptides directly incorporate into tissue collagen or act as signaling molecules that upregulate endogenous synthesis. Isotope tracer studies could clarify this but have not been widely conducted.
Comparison to dietary protein has not been rigorously tested. Collagen is low in tryptophan and other essential amino acids. Whether collagen peptides offer advantages over an equivalent dose of complete protein remains uncertain.
Long-term use beyond six months has not been studied in most populations. Safety and sustained efficacy are assumed but not demonstrated.
Individuals vary in baseline collagen synthesis rates, dietary protein intake, and degradation pathways. This variability likely explains the range of responses seen in both trials and clinical use.
Practical Considerations
Collagen supplements are most commonly used by individuals seeking to slow visible aging, manage joint discomfort, or support recovery from injury. Expectations should align with trial evidence.
Skin aging involves photoaging, glycation, and hormonal changes in addition to collagen loss. Supplementation is one intervention among many, including sun protection, topical retinoids, and systemic treatments that address inflammation and oxidative stress. Regenerative treatments such as exosome therapy or peptide protocols may offer complementary pathways.
Joint pain from osteoarthritis or overuse may respond to collagen peptides, but weight management, physical therapy, and anti-inflammatory strategies remain first-line. Supplements are adjuncts, not replacements.
Athletic recovery protocols increasingly include collagen, often combined with vitamin C and taken post-exercise. The rationale is tendon and ligament support, but controlled data in high-performance populations are limited.
Cost varies widely. Products range from 500 to 3,000 baht per month depending on dose, source, and brand. Third-party testing and transparent sourcing add cost but improve confidence in purity.
Taste and palatability affect adherence. Unflavored powders mix into liquids but have a mild odor. Flavored versions contain sweeteners. Capsules eliminate taste but require higher pill counts to reach effective doses.
Physician Oversight
Collagen supplements are available without prescription, but incorporating them into a structured health program requires clinical context. Physicians can assess baseline collagen-related markers, screen for contraindications, and monitor for interactions with other interventions.
Baseline testing might include markers of bone turnover, inflammatory markers (hsCRP), and skin hydration if quantitative tracking is desired. Imaging (DEXA for bone, ultrasound for tendons) provides structural baselines.
Medication interactions are minimal. Collagen does not interfere with anticoagulants, statins, or common pharmaceuticals. However, individuals on antiplatelet therapy or with bleeding disorders should discuss bovine or marine sources with a physician due to theoretical but unproven risk.
Allergies and intolerances to source proteins require substitution. Marine collagen may be unsuitable for those with fish allergies. Bovine and porcine sources present religious or dietary restrictions for some individuals.
Monitoring involves reassessment at 12 and 24 weeks if objective measures are used. Subjective improvement without measurable change may reflect placebo response or concurrent lifestyle modifications.
For individuals enrolled in longer-term longevity programs that track 100 or more biomarkers, collagen supplementation can be one element in a protocol addressing tissue aging, alongside interventions targeting inflammation, glycation, and cellular senescence.
Frequently Asked Questions
How long does it take to see results from collagen supplements?
Skin hydration changes may appear by 8 weeks. Joint pain reduction typically requires 12 to 24 weeks. Individual response varies, and no effect may occur in some people despite adherence.
Can collagen supplements replace dietary protein?
No. Collagen peptides lack adequate tryptophan and other essential amino acids. They supplement but do not substitute for complete protein sources such as meat, fish, eggs, or legumes.
Are marine or bovine collagen peptides more effective?
Trials have not shown consistent differences in bioavailability or outcomes between sources when peptide size and dose are matched. Choice often depends on dietary preference or allergen concerns.
Do collagen supplements need to be taken with vitamin C?
Vitamin C is required for collagen synthesis in the body. Co-supplementation is common in trials, though isolated collagen has also shown effects. Adequate dietary vitamin C (75 to 90 mg per day) is sufficient for most individuals.
Collagen supplements offer measurable support for skin hydration and joint comfort in some individuals when used at trial-tested doses for adequate durations. Response is not universal, and long-term data are limited. Healthi Life provides physician-led assessment of skin, joint, and metabolic markers through diagnostic protocols that place supplementation within a broader longevity strategy, supervised from baseline through re-testing and adjustment. Book a consultation at Healthi Life.
This page is for information only and is not medical advice. Medical consultation and prescription are available online and on site at Healthi Life, Ekkamai, Bangkok.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
