
Lipoprotein A: What the Number Means and When to Test
Lipoprotein a elevates cardiovascular risk independently of LDL. Measure it once; the value remains stable. Learn when testing matters.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
Lipoprotein a is a cholesterol-carrying particle found in blood. Its concentration is determined almost entirely by genetic inheritance and remains stable throughout adult life. Elevated lipoprotein a increases cardiovascular risk independently of LDL cholesterol, and no medication is approved specifically to lower it (as of September 2026). Measurement is recommended once, typically during a comprehensive cardiovascular risk assessment.
Key takeaways
- Lipoprotein(a) is a cholesterol-carrying particle whose level is set mostly by genetics and stays stable through adult life.
- A high level raises cardiovascular risk independently of LDL cholesterol.
- The 2022 European Atherosclerosis Society consensus recommends measuring it at least once in every adult.
- Diet and exercise do not change it meaningfully; management focuses on controlling the other, modifiable risk factors.
- One test is usually enough, because the value rarely changes.
Updated 26 September 2026. Reviewed against the published literature cited below.
What Lipoprotein A Is and How It Differs From LDL
Lipoprotein a is a low-density lipoprotein particle with an additional protein component called apolipoprotein(a) attached to it. This structural difference distinguishes it from standard LDL cholesterol. Healthi Life is a physician-led longevity clinic in Bangkok.
Particle Structure
The particle consists of:
- An LDL-like lipid core containing cholesterol and triglycerides
- Apolipoprotein B-100, the same protein found in LDL
- Apolipoprotein(a), a large glycoprotein unique to lipoprotein a
Apolipoprotein(a) varies in size between individuals due to genetic variation in the LPA gene. Smaller isoforms correlate with higher particle concentrations in circulation.
Genetic Determination
Lipoprotein a concentration is predominantly genetically determined. Diet, exercise, and most lipid-lowering medications produce negligible changes. This stability means a single measurement is sufficient for risk stratification in most adults.

Cardiovascular Risk and Clinical Evidence
Elevated lipoprotein a is associated with increased risk of myocardial infarction, stroke, aortic stenosis, and peripheral arterial disease. The relationship is continuous, without a clear threshold below which risk disappears.
In a UK Biobank study of 460,506 middle-aged adults, the link between lipoprotein a and atherosclerotic cardiovascular disease appeared linear across the whole distribution, with a hazard ratio of 1.11 per 50 nmol/L increase. A concentration of 150 nmol/L or higher was found in 12.2 percent of participants without prior cardiovascular disease and was associated with a hazard ratio of 1.50 (Patel et al., 2021).
Risk amplification is greater when other risk factors are present. In individuals with familial hypercholesterolemia, elevated lipoprotein a compounds risk substantially.
Mechanisms of Harm
Lipoprotein a may promote atherosclerosis through several pathways:
- Deposition of cholesterol in arterial walls
- Pro-inflammatory effects on endothelial cells
- Possible antifibrinolytic effects, although the 2022 European Atherosclerosis Society consensus found that current evidence does not support impaired fibrinolysis or venous thrombosis as clinical effects
- Oxidized phospholipids carried on the particle contribute to plaque formation
These mechanisms remain under investigation. No single pathway has been confirmed as dominant.
When to Measure Lipoprotein A
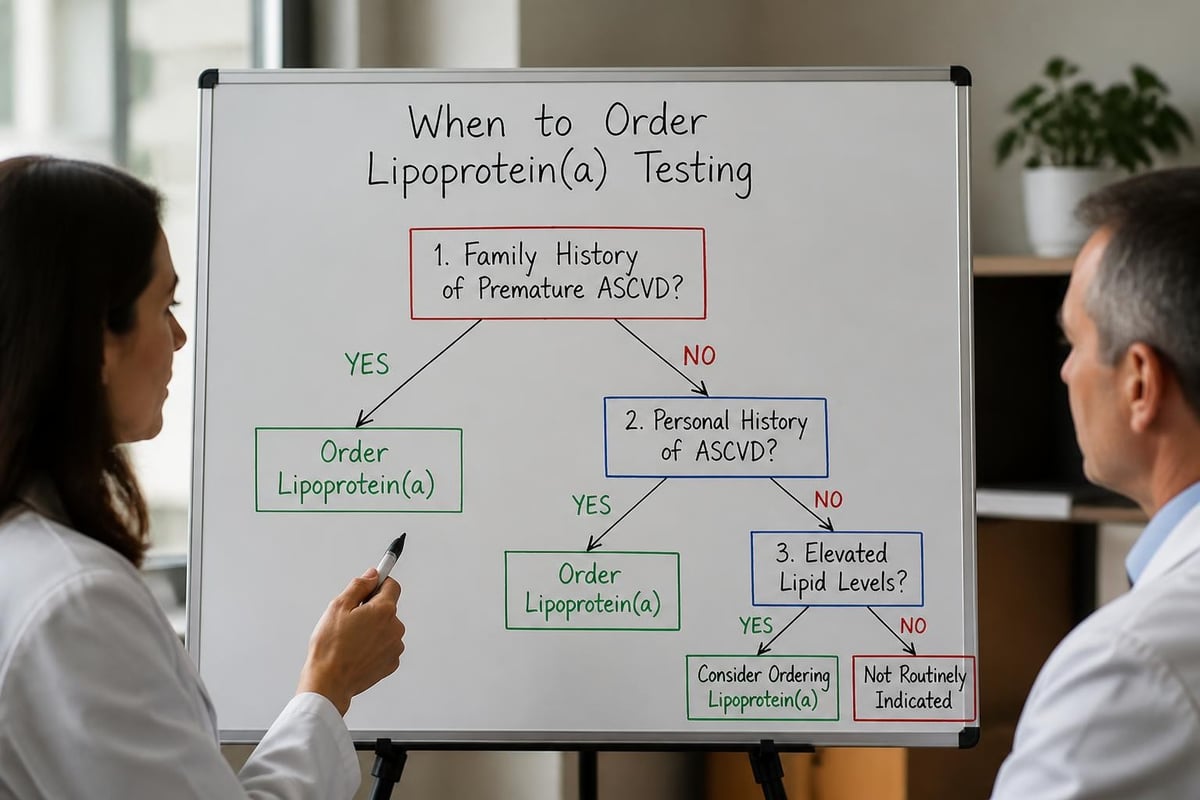
The 2022 European Atherosclerosis Society consensus recommends measuring lipoprotein a at least once in all adults. Testing matters most in people with a personal or family history of premature cardiovascular disease, elevated LDL despite treatment, or recurrent cardiovascular events. An update on lipoprotein a from the American College of Cardiology summarizes current clinical guidance.
Indications for Testing
- First-degree relative with myocardial infarction or stroke before age 55 (men) or 65 (women)
- Personal history of atherosclerotic cardiovascular disease before age 60
- Familial hypercholesterolemia or LDL cholesterol persistently above target despite statin therapy
- Recurrent cardiovascular events despite guideline-directed medical therapy
Recommendations differ: European and Canadian societies advise at least one measurement in every adult, while the 2018 ACC/AHA cholesterol guideline focuses on people with increased risk. The test is most useful when the result will influence clinical decision-making.
Measurement Methodology
Lipoprotein a is measured in mg/dL or nmol/L. The two units are not directly interchangeable because apolipoprotein(a) size varies. Interlaboratory comparison and standardization efforts published in 2025 describe ongoing variability across assays and steps toward harmonization.
Most laboratories report values in mg/dL. A concentration above 50 mg/dL is generally considered elevated, though risk increases continuously above 30 mg/dL.
Treatment and Management Options
No medication has been approved specifically to lower lipoprotein a. Statins do not reduce the particle concentration and may slightly increase it in some individuals. Niacin lowers lipoprotein a modestly but has not been shown to reduce cardiovascular events when added to statin therapy.
Current Approaches
Management focuses on addressing modifiable risk factors:
- LDL cholesterol reduction: Lower LDL to compensate for the additional risk from elevated lipoprotein a
- Blood pressure control: Target systolic blood pressure below 130 mmHg in most adults
- Glycemic control: Maintain HbA1c below 7.0 percent in individuals with diabetes
- Lifestyle modification: Cessation of tobacco use, regular aerobic exercise, Mediterranean-pattern diet
PCSK9 inhibitors lower lipoprotein a modestly as a secondary effect while substantially reducing LDL cholesterol. The reduction in lipoprotein a may contribute to clinical benefit, but this has not been proven.
Investigational Therapies
Antisense oligonucleotides targeting hepatic LPA mRNA have lowered lipoprotein a substantially in trials, and small interfering RNA agents have produced similar or larger reductions. A reduction in cardiovascular events has not been demonstrated, and none of these agents is approved for clinical use as of September 2026.
The absence of approved therapies does not mean the measurement lacks value. Knowing the result informs intensity of LDL reduction and overall cardiovascular prevention strategy.
Lipoprotein A in the Context of Comprehensive Risk Assessment
Lipoprotein a is one component of cardiovascular risk. It does not operate in isolation. A comprehensive evaluation integrates lipid markers, inflammatory markers, imaging, and family history.
Advanced diagnostic assessments include lipoprotein a alongside apolipoprotein B, oxidized LDL, high-sensitivity C-reactive protein, and coronary artery calcium scoring. Which of these markers to add is decided with the physician, according to personal and family history.
Biomarkers Measured in Cardiovascular Panels
| Biomarker | What It Reflects | Clinical Use |
|---|---|---|
| Lipoprotein a | Genetic cardiovascular risk | One-time measurement |
| Apolipoprotein B | Total atherogenic particle number | Superior to LDL-C in some contexts |
| Oxidized LDL | Oxidative stress in lipid particles | Research use, limited clinical data |
| High-sensitivity CRP | Systemic inflammation | Residual risk assessment |
| Coronary artery calcium | Presence and extent of calcified plaque | Reclassifies people at intermediate risk |
These markers are interpreted by a physician who reviews the full clinical picture, not as isolated values.
Integration With Other Risk Factors
Lipoprotein a interacts with traditional risk factors. An individual with elevated lipoprotein a and optimal LDL, blood pressure, and glucose may have lower absolute risk than someone with borderline lipoprotein a and multiple poorly controlled risk factors.
The decision to intensify therapy depends on total risk, not a single biomarker. This is where physician interpretation becomes essential.

Who Should Consider Lipoprotein A Testing
Testing is appropriate for individuals who meet clinical criteria and are prepared to act on the result. The measurement is most informative when family history suggests genetic dyslipidemia or when unexplained cardiovascular events occur despite controlled conventional risk factors.
Populations With Higher Prevalence
Prevalence of elevated lipoprotein a varies by ancestry:
- In the UK Biobank, median concentrations were 75 nmol/L in Black participants, 31 nmol/L in South Asian participants, 19 nmol/L in white participants, and 16 nmol/L in Chinese participants
- The risk associated with each 50 nmol/L increase appeared similar across these groups
These differences are genetic. Lifestyle has little effect on lipoprotein a concentration.
Cascade Screening
When an individual is found to have markedly elevated lipoprotein a (above 100 mg/dL), first-degree relatives may be tested. Because lipoprotein a levels are inherited, first-degree relatives of a person with high lipoprotein a are more likely to have high levels themselves, which is why the European Atherosclerosis Society sees value in cascade testing.
Cascade screening is not universal practice but may be considered when the index case has experienced early cardiovascular events.
Stability and Retesting
Lipoprotein a remains stable throughout adulthood. A single measurement is sufficient. Repeat testing is not indicated unless the initial result is borderline and clinical circumstances change substantially.
Pregnancy, acute illness, and inflammation may transiently alter lipoprotein a concentration, but the effect is small compared to genetic variation. Timing the test during stable health is preferred.
Lipoprotein A and Long-Term Health Strategy
Elevated lipoprotein a does not mean cardiovascular disease is inevitable. It means additional vigilance is warranted. The goal is to lower total cardiovascular risk by controlling modifiable factors.
Steps Following an Elevated Result
- Physician consultation: Discuss the result in the context of family history, lipid panel, blood pressure, and metabolic health
- Intensify LDL reduction: Aim for LDL cholesterol below 70 mg/dL, or lower if very high risk
- Imaging: Consider coronary artery calcium scoring if risk category is uncertain
- Lifestyle modification: Mediterranean diet, regular aerobic exercise, tobacco cessation
- Monitor compliance: Reassess lipid panel and blood pressure at six- to twelve-month intervals
These steps are implemented under medical supervision. Self-directed adjustment of medication is not appropriate.
Frequently Asked Questions
Does diet affect lipoprotein a concentration?
No. Dietary changes do not significantly alter lipoprotein a levels. The particle concentration is genetically determined and remains stable regardless of macronutrient intake or calorie balance.
Should I take niacin to lower lipoprotein a?
Niacin lowers lipoprotein a modestly but has not been shown to reduce cardiovascular events when added to statin therapy. Its use is not recommended solely for lipoprotein a reduction. The decision requires physician consultation.
How often should lipoprotein a be retested?
Once. The value does not change meaningfully in adulthood. Repeat testing is not necessary unless the first result was obtained during acute illness or pregnancy and needs confirmation.
Can exercise lower lipoprotein a?
No. Aerobic exercise improves cardiovascular health through multiple mechanisms but does not reduce lipoprotein a concentration. Exercise remains beneficial for lowering blood pressure, improving insulin sensitivity, and reducing overall cardiovascular risk.
Access to Testing and Physician Interpretation
Lipoprotein a is measured through standard venous blood sampling. Most clinical laboratories offer the test, though it is not included in routine lipid panels. Ordering requires physician request.
Lipoprotein(a) is one of the markers a physician can discuss when planning a health check-up or an executive health assessment.
Results are returned as a numerical concentration. The number has no meaning without clinical context. Family history, personal cardiovascular history, and concurrent risk factors determine whether the result changes management.
Physician review is essential. A result of 60 mg/dL in a 50-year-old with no other risk factors may lead to lifestyle counseling and baseline imaging. The same result in a 50-year-old with familial hypercholesterolemia and a father who experienced myocardial infarction at age 48 may prompt aggressive LDL reduction and consideration for advanced imaging or cardiology referral.
This interpretation is not formulaic. It requires clinical judgment.
Lipoprotein a is a genetically determined cardiovascular risk marker that is measured once and informs long-term prevention strategy. Elevated levels warrant intensified management of modifiable risk factors, under physician supervision. If you are evaluating your cardiovascular risk profile or building a long-term health protocol, Healthi Life offers physician-led biomarker assessments and continuous medical oversight in Bangkok.
This page is for information only and is not medical advice. Medical consultation and prescription are available online and on site at Healthi Life, Ekkamai, Bangkok.
