
Metabolic Syndrome: Definition, Diagnosis & Management

Metabolic syndrome in 2026: diagnostic criteria, biomarker testing, and physician-supervised protocols for HNW residents in Bangkok.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. GLP-1 medication (semaglutide — Ozempic, Wegovy; tirzepatide — Mounjaro) is a prescription medicine, dispensed and administered only after assessment by a licensed physician. This page is medical information, not an advertisement or an offer of treatment. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
Metabolic syndrome is a cluster of five measurable conditions that appear together and raise the risk of cardiovascular disease, type 2 diabetes, and premature mortality. A physician diagnoses metabolic syndrome when at least three of these conditions are present: elevated waist circumference, raised blood pressure, elevated fasting glucose, high triglycerides, and low HDL cholesterol. The National Heart, Lung, and Blood Institute defines the syndrome as a clinical identifier rather than a single disease, and the diagnosis requires laboratory confirmation alongside physical measurement.
What Metabolic Syndrome Is and How It Is Defined
Metabolic syndrome describes a pattern of abnormalities that cluster in the same person. No single cause explains the syndrome. Insulin resistance, visceral adiposity, chronic inflammation, and genetic predisposition all contribute.
A 2024 Disease Primer published in Nature confirms that metabolic syndrome prevalence has risen in parallel with obesity worldwide. The syndrome is not static. A person may meet diagnostic criteria at one assessment and fall below the threshold after intervention.
The Five Diagnostic Components
Physicians use standardized thresholds for each component. These criteria come from consensus statements issued by the International Diabetes Federation and other professional bodies.
| Component | Threshold (adults) | Measurement |
|---|---|---|
| Waist circumference | ≥90 cm (men), ≥80 cm (women, Asian population) | Measured at midpoint between lowest rib and iliac crest |
| Blood pressure | ≥130/85 mmHg or on antihypertensive medication | Seated, rested, standardized cuff |
| Fasting glucose | ≥5.6 mmol/L or on glucose-lowering medication | Venous plasma, fasted 8-12 hours |
| Triglycerides | ≥1.7 mmol/L or on lipid medication | Venous plasma, fasted |
| HDL cholesterol | <1.0 mmol/L (men), <1.3 mmol/L (women) | Venous plasma, fasted |
Diagnosis requires three or more components present at the same time. A single borderline result does not confirm the syndrome.

Variations in Diagnostic Criteria
Different organizations publish slightly different thresholds. The International Diabetes Federation emphasizes central obesity as a mandatory criterion. The Adult Treatment Panel III (ATP III) does not require waist circumference but counts it as one of five equal criteria.
Asian populations have lower waist-circumference cutoffs than European populations. This adjustment reflects higher cardiometabolic risk at lower BMI and waist values in Asian individuals. The IDF consensus materials provide region-specific thresholds, and most Bangkok-based physicians apply the Asian cutoffs.
Why Metabolic Syndrome Matters for Long-Term Health
The syndrome increases the risk of major clinical events. A meta-analysis of prospective cohort studies found that people with metabolic syndrome have approximately double the risk of cardiovascular events and 1.5 times the risk of all-cause mortality compared with those who do not meet diagnostic criteria.
Type 2 diabetes incidence rises five-fold in people with metabolic syndrome. Progression to diabetes is not inevitable. Weight reduction, exercise, and pharmacotherapy can reverse individual components and lower the composite risk.
Cardiovascular Consequences
Atherosclerosis accelerates when multiple risk factors coexist. Endothelial dysfunction, low-grade inflammation, and dyslipidemia all contribute to plaque formation. Coronary artery disease, myocardial infarction, and stroke are the primary cardiovascular outcomes associated with the syndrome.
Blood pressure and lipid abnormalities independently predict cardiovascular events. When both are present, the risk compounds. Physicians assess ten-year cardiovascular risk using validated calculators that incorporate age, sex, smoking status, and biomarker values.
Hepatic and Renal Involvement
Non-alcoholic fatty liver disease (NAFLD) is common in people with metabolic syndrome. Hepatic steatosis develops when insulin resistance promotes lipid accumulation in hepatocytes. A minority progress to non-alcoholic steatohepatitis (NASH), fibrosis, and cirrhosis.
Chronic kidney disease prevalence is higher in people with metabolic syndrome. Hypertension and hyperglycemia damage glomerular filtration over years. Measuring cystatin C and calculating estimated glomerular filtration rate (eGFR) provide earlier detection than creatinine alone.
How Metabolic Syndrome Is Diagnosed in Practice
Diagnosis requires both measurement and interpretation. A physician orders a fasting blood panel, records blood pressure and anthropometric data, and reviews medication history. The diagnosis is made when three or more criteria are met.
Standard diagnostic workup includes:
- Waist circumference measured at the narrowest point between ribs and iliac crest
- Blood pressure taken after five minutes seated rest
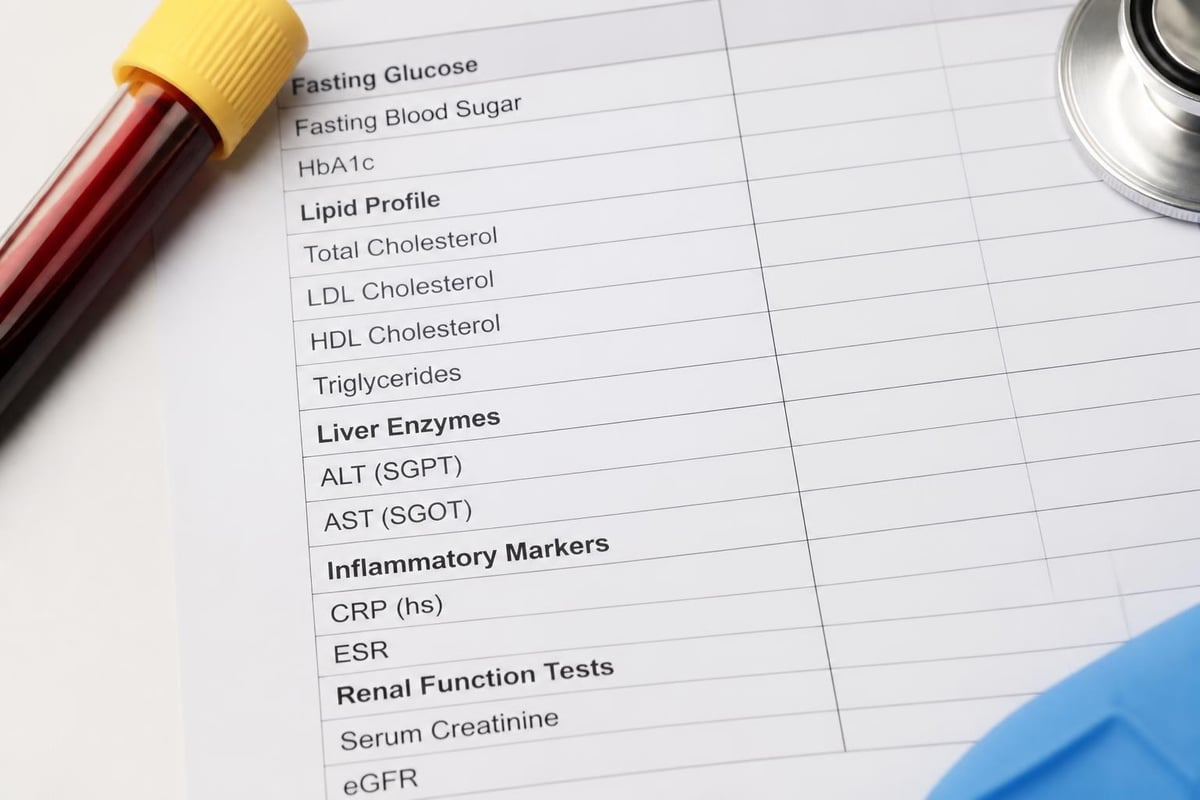
- Fasting glucose, triglycerides, total cholesterol, HDL cholesterol, and LDL cholesterol
- HbA1c to assess average glucose over the preceding three months
- Liver function tests (ALT, AST) to screen for NAFLD
Additional biomarkers add context. High-sensitivity C-reactive protein (hs-CRP) indicates systemic inflammation. Apolipoprotein B (ApoB) quantifies atherogenic particle number and predicts cardiovascular risk more accurately than LDL cholesterol in some cohorts.
Advanced Testing and Continuous Monitoring
Annual screening captures trend direction but misses intra-year variation. For people at high risk or undergoing intervention, quarterly biomarker panels track response and guide protocol adjustment.
An Advanced Check-Up provides a structured baseline that includes biomarker panels, imaging, and DNA testing. Results are reviewed one-to-one with a physician, who decides whether metabolic syndrome criteria are met and whether additional investigation is warranted. This is the entry point for people who want diagnostic clarity before committing to a supervised intervention.
Evidence-Based Interventions That Reverse the Syndrome
Metabolic syndrome is reversible. Weight reduction of 5 to 10 percent of baseline body weight improves all five components in most people. Exercise, independent of weight loss, enhances insulin sensitivity and raises HDL cholesterol.
An open-access review in PubMed Central summarizes current best practices for primary care clinicians. The hierarchy of intervention begins with lifestyle modification, followed by pharmacotherapy when lifestyle alone is insufficient.
Dietary Approaches Supported by Trial Data
No single diet reverses metabolic syndrome in all people. Mediterranean, low-carbohydrate, and calorie-restricted diets all show benefit in randomized controlled trials. The common elements are reduction in refined carbohydrate, emphasis on whole foods, and caloric deficit when weight loss is the goal.
- Mediterranean diet: Rich in monounsaturated fats, fiber, and polyphenols. Reduces triglycerides and raises HDL.
- Low-carbohydrate diet: Lowers fasting glucose and insulin. Effective for weight reduction in the short term.
- Calorie restriction: Produces weight loss and improves all metabolic components when adherence is sustained.
Adherence matters more than the specific dietary pattern chosen. A physician reviews baseline labs, food preferences, and metabolic goals before recommending a protocol. Re-testing at three months shows which parameters have improved.
Exercise Prescription Based on Physiology
Aerobic exercise improves cardiovascular fitness and insulin sensitivity. Resistance training increases muscle mass, which raises resting metabolic rate and glucose disposal. Combining both modalities produces additive benefit.
The American Heart Association recommends at least 150 minutes of moderate-intensity aerobic activity per week, plus muscle-strengthening activities on two or more days. High-intensity interval training (HIIT) delivers similar metabolic improvements in shorter sessions, but cardiovascular screening is advised before starting HIIT in previously sedentary adults.
Pharmacotherapy for Persistent Risk Factors
When lifestyle intervention does not normalize biomarkers, medication is indicated. Statins lower LDL cholesterol and reduce cardiovascular events. ACE inhibitors and angiotensin receptor blockers control blood pressure and protect renal function. Metformin reduces fasting glucose and lowers progression to type 2 diabetes.
GLP-1 receptor agonists produce weight loss, lower HbA1c, and reduce cardiovascular events in people with type 2 diabetes. Trials in people with metabolic syndrome but without diabetes are ongoing. Tirzepatide side effects are dose-dependent and include nausea, vomiting, and gastrointestinal discomfort. A physician adjusts the dose based on tolerance and response.
Sleep, Stress, and Metabolic Health
Short sleep duration and poor sleep quality worsen insulin resistance and increase appetite-regulating hormone dysregulation. Adults who sleep less than six hours per night have higher rates of metabolic syndrome than those who sleep seven to eight hours.
Obstructive sleep apnea (OSA) is common in people with central obesity. OSA causes intermittent hypoxia, which activates the sympathetic nervous system and raises blood pressure. Polysomnography diagnoses OSA, and continuous positive airway pressure (CPAP) therapy improves both sleep quality and metabolic parameters.
Strategies to improve sleep quality:
- Maintain a consistent sleep-wake schedule, including weekends
- Limit screen exposure in the two hours before bed
- Keep the bedroom dark, quiet, and cool (18-20°C)
- Avoid caffeine after midday and alcohol within three hours of sleep
How to get more deep sleep discusses evidence-based protocols for improving sleep architecture. Deep sleep is the phase during which growth hormone is secreted and metabolic restoration occurs.
Chronic stress elevates cortisol, which promotes visceral fat accumulation and insulin resistance. Mindfulness-based stress reduction, cognitive behavioral therapy, and regular physical activity all lower perceived stress and improve metabolic outcomes in controlled trials.
Biomarker Tracking and Protocol Adjustment
Single-point measurement reveals current status. Serial measurement reveals trajectory and intervention response. A physician interprets biomarker trends in the context of medication changes, weight fluctuation, exercise adherence, and sleep quality.
| Biomarker | Baseline | 3 months | 6 months | Target |
|---|---|---|---|---|
| Fasting glucose (mmol/L) | 6.2 | 5.8 | 5.4 | <5.6 |
| HbA1c (%) | 6.0 | 5.7 | 5.5 | <5.7 |
| Triglycerides (mmol/L) | 2.4 | 1.9 | 1.5 | <1.7 |
| HDL cholesterol (mmol/L) | 0.9 | 1.0 | 1.1 | >1.0 |
| Waist circumference (cm) | 96 | 92 | 88 | <90 |
Quarterly re-testing allows protocol refinement. If triglycerides remain elevated despite dietary change, a physician may add a fibrate. If weight loss stalls, the exercise prescription is adjusted or a GLP-1 agonist is considered.

Longevity programs at Healthi Life run three to twelve months and are built on up to 300 biomarkers. Continuous medical supervision means the physician reviews lab results as they arrive and adjusts the protocol without waiting for the next scheduled visit. This is how metabolic syndrome reversal is managed in people who want active oversight rather than annual check-ins.
Frequently Asked Questions
Can metabolic syndrome be reversed completely?
Yes. Weight reduction, exercise, and pharmacotherapy can normalize all five diagnostic components. Once reversed, the syndrome may recur if weight is regained or lifestyle changes are not sustained. Long-term maintenance requires ongoing adherence.
How quickly do biomarkers improve after starting intervention?
Fasting glucose and triglycerides often improve within four to six weeks. HDL cholesterol rises more slowly, over three to six months. Blood pressure responds within weeks to weight loss and sodium restriction. HbA1c reflects average glucose over three months, so change lags behind fasting glucose.
Is metabolic syndrome the same as insulin resistance?
No. Insulin resistance is a physiological state in which cells respond poorly to insulin. Metabolic syndrome is a clinical diagnosis based on five criteria. Insulin resistance underlies most cases of metabolic syndrome, but the syndrome is defined by measurable thresholds, not insulin sensitivity directly.
Do I need medication if I meet the diagnostic criteria?
Not always. If lifestyle intervention normalizes biomarkers within three to six months, medication may not be required. A physician decides based on absolute risk, family history, and response to initial intervention. Statins and antihypertensives reduce cardiovascular events even when lifestyle changes are effective.
Why a Physician-Led Approach Matters
Self-directed intervention is possible, but physician supervision improves outcomes. A doctor interprets lab results in clinical context, prescribes medication when indicated, adjusts doses based on tolerance, and monitors for complications.
MedlinePlus provides patient-facing education on metabolic syndrome. It explains what each component means and lists resources for diet and exercise. It does not replace individualized assessment.
Longevity medicine treats health as a continuous program, not a series of isolated check-ups. Biomarkers are measured frequently. Protocols are adjusted as data arrive. The physician sees the trend before the patient feels the change. This is the model used in supervised longevity programs, where the goal is not symptom relief but measurable risk reduction over years.
What Happens When Metabolic Syndrome Is Left Untreated
Untreated metabolic syndrome progresses. Insulin resistance worsens. Beta-cell function declines. Type 2 diabetes develops. Atherosclerosis accelerates. Kidney function deteriorates. The time from diagnosis to clinical event varies, but the trajectory is consistent.
Some people with metabolic syndrome remain asymptomatic for years. Absence of symptoms does not mean absence of risk. Coronary artery disease is often silent until myocardial infarction. Chronic kidney disease is asymptomatic until glomerular filtration rate falls below 30 mL/min/1.73 m².
Early intervention reduces long-term risk more effectively than late intervention. A ten-year delay in diagnosis means a decade of endothelial damage, hepatic lipid accumulation, and beta-cell stress. Reversal is still possible, but the starting point is worse and the intervention more intensive.
Integrating Metabolic Syndrome Reversal Into a Longevity Framework
Longevity medicine prioritizes healthspan, not lifespan alone. Metabolic syndrome shortens both. Reversing the syndrome is foundational. Once biomarkers normalize, the focus shifts to optimization: mitochondrial function, cellular senescence, inflammatory balance, and micronutrient sufficiency.
Advanced biomarker panels include oxidative stress markers, omega-3 index, homocysteine, and vitamin D. DNA methylation testing estimates biological age. Continuous glucose monitors track glycemic variability in real time, even when HbA1c is normal.
These tools are not diagnostic in the traditional sense. They inform protocol design. A physician reviews the full dataset, identifies modifiable variables, and prescribes a sequence of interventions. Re-testing shows which variables moved and by how much.
This is the difference between treating disease and optimizing health. Metabolic syndrome reversal is the first step. The next steps depend on the person's goals, baseline data, and response trajectory.
Metabolic syndrome is diagnosed when three or more of five criteria are present, and it is reversible through weight reduction, exercise, and pharmacotherapy when lifestyle alone is insufficient. A physician interprets biomarker trends, prescribes intervention, and re-tests at intervals that match the protocol's intensity. Healthi Life offers physician-supervised longevity programs in Ekkamai, Bangkok, built on up to 300 biomarkers and continuous medical oversight, for people who want their metabolic health managed as an ongoing program rather than an annual check.
This page is for information only and is not medical advice. Medical consultation and prescription are available online and on site at Healthi Life, Ekkamai, Bangkok.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
