
Tesamorelin: Mechanism, Evidence, and Clinical Use
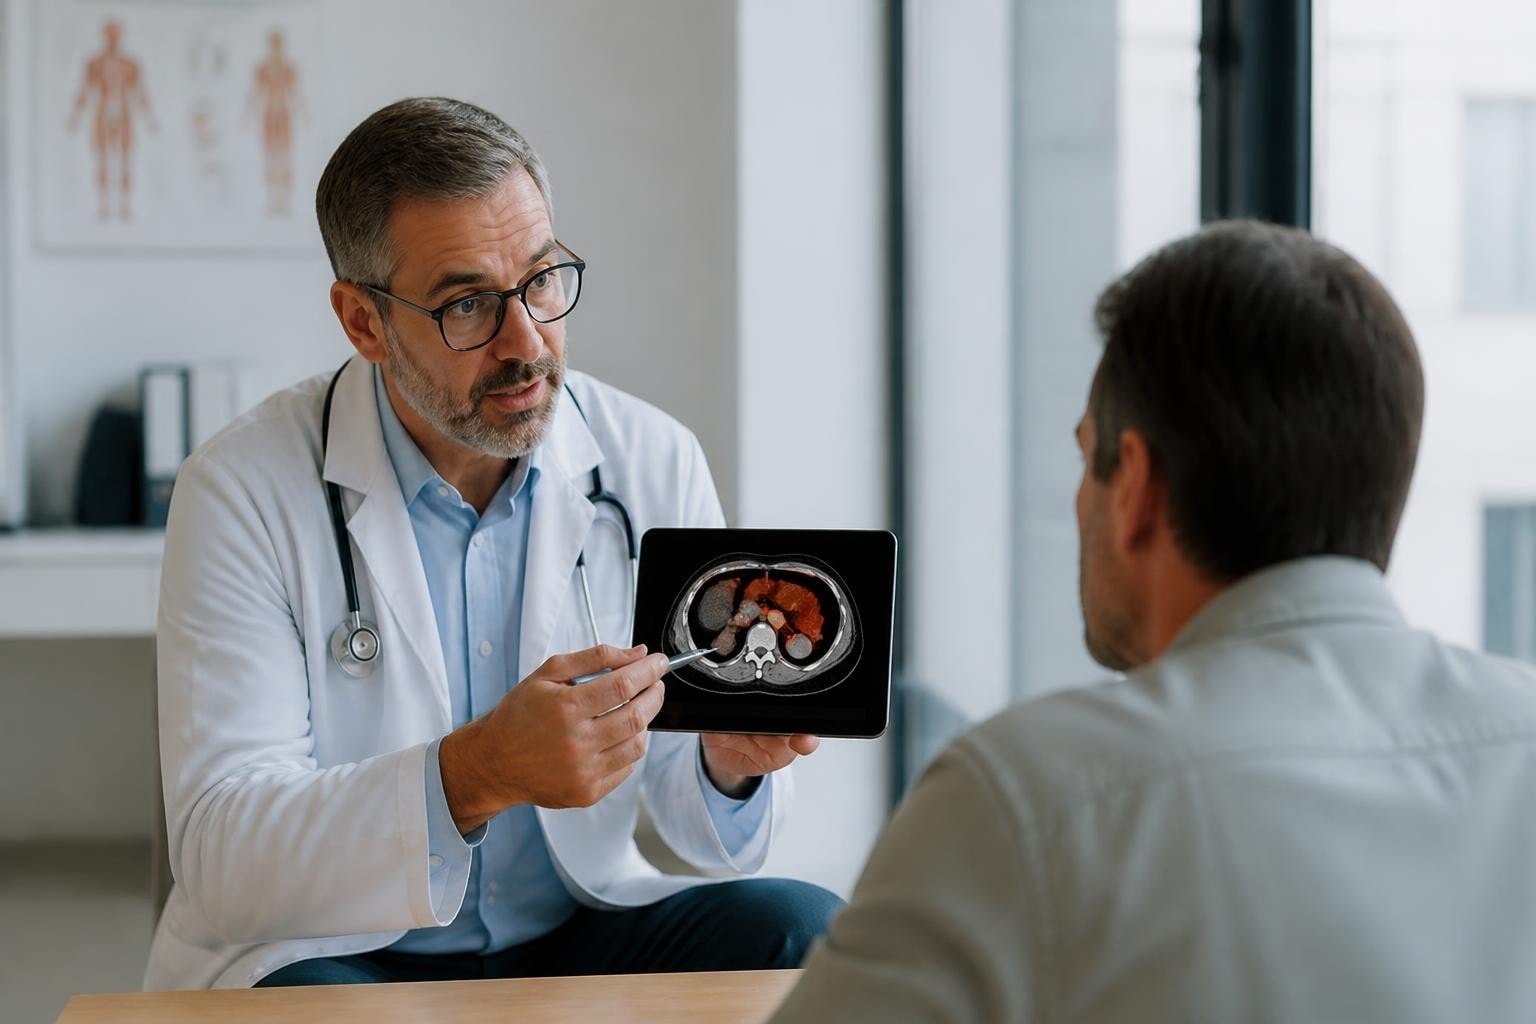
What tesamorelin does, how it works, and which populations have been studied. Evidence from FDA trials, regulatory decisions, and metabolic data.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
Tesamorelin is a synthetic analog of growth hormone-releasing hormone. It was approved by the FDA in 2010 for the reduction of excess visceral adipose tissue in adults with HIV-associated lipodystrophy. The peptide consists of 44 amino acids with a trans-3-hexenoic acid group attached to enhance stability and half-life. Clinical trials that led to approval focused on a single indication. Use outside that population remains investigational. Physicians assess whether tesamorelin is appropriate based on imaging, metabolic biomarkers, and individual risk factors.
What Tesamorelin Does in the Body
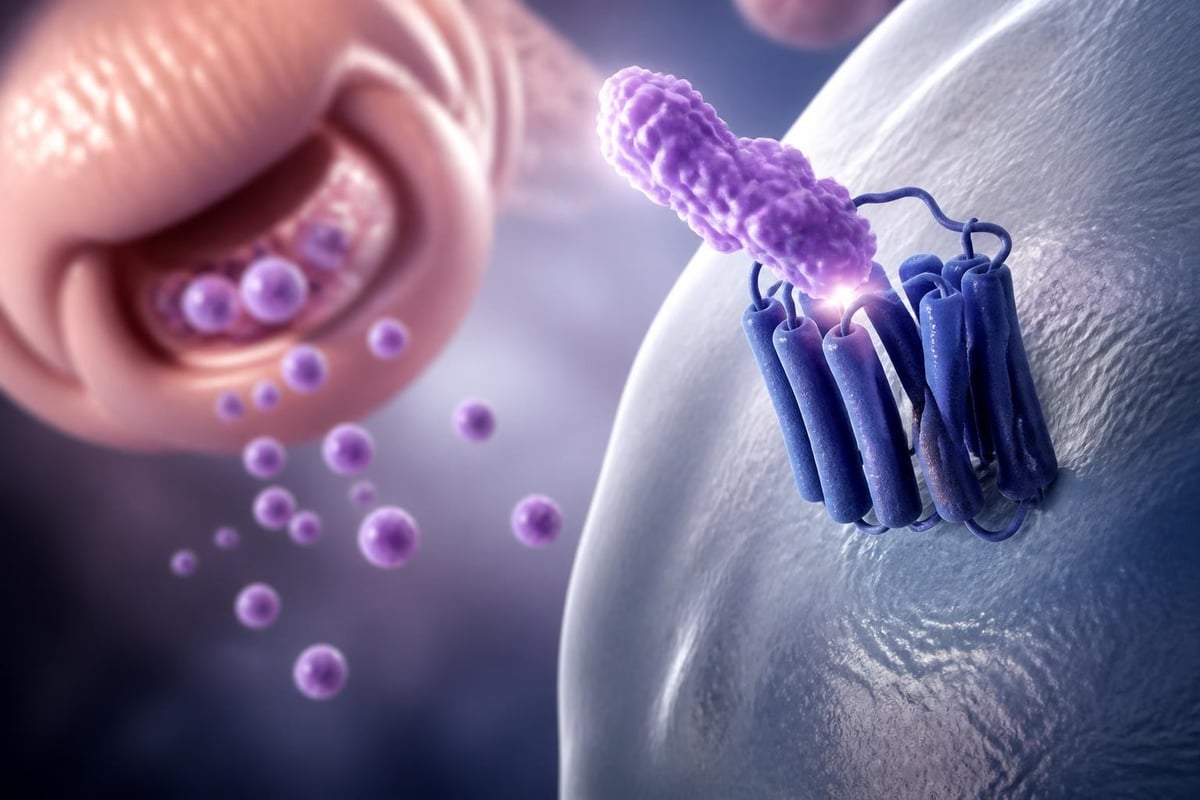
Tesamorelin binds to GHRH receptors on somatotrophs in the anterior pituitary. This triggers the release of endogenous growth hormone in a pulsatile pattern. Growth hormone then stimulates hepatic and peripheral production of insulin-like growth factor 1. The GHRH/GH/IGF-1 axis governs multiple metabolic processes including lipolysis, glucose homeostasis, and lean mass maintenance. Healthi Life is a physician-led longevity clinic in Bangkok.
Tesamorelin does not introduce exogenous growth hormone. It increases the body's own secretion. This distinction matters for both safety and regulatory classification. The peptide is cleared within hours. Its effects depend on repeated dosing to maintain GHRH receptor stimulation.
Visceral Adipose Tissue Reduction
The primary clinical endpoint in FDA trials was change in visceral adipose tissue area measured by computed tomography. At 26 weeks, mean VAT changed by -18% and -14% with tesamorelin in the two trials, compared with +2% and -2% with placebo. These findings are detailed in the FDA-approved prescribing information.
VAT is metabolically distinct from subcutaneous fat. It releases inflammatory cytokines, free fatty acids, and adipokines that contribute to insulin resistance, hepatic steatosis, and cardiovascular risk. Reduction in VAT can improve metabolic markers even when total body weight changes minimally.
Tesamorelin does not target subcutaneous fat to the same degree. Limb fat and overall body mass index showed small changes in trials. The effect is specific to intra-abdominal depots.
Metabolic Markers and Lipid Profiles
Secondary endpoints in pivotal trials included lipid and glucose parameters. Triglyceride levels decreased in the tesamorelin group. Changes in LDL and HDL cholesterol were inconsistent across studies. Tesamorelin can cause glucose intolerance: by week 26, 5% of tesamorelin-treated and 1% of placebo-treated participants had an HbA1c of 6.5% or higher.
Physicians monitor lipid panels, glucose, and HbA1c before initiation and at regular intervals. Diagnostic baselines guide the decision to continue or adjust.
Who Has Been Studied
All FDA-approved trials enrolled adults with HIV who had lipodystrophy confirmed by clinical assessment and imaging. Lipodystrophy in this population results from antiretroviral therapy and the virus itself. Fat accumulates centrally while subcutaneous depots atrophy. This pattern increases metabolic risk and affects quality of life.
Tesamorelin is not approved for general obesity, metabolic syndrome, or cosmetic fat reduction. Use in these contexts remains off-label and investigational.
Trial Design and Duration
The two pivotal trials were randomized, double-blind, and placebo-controlled. They lasted 26 weeks. A long-term extension study followed participants for an additional 26 weeks. The extension showed that VAT reduction was maintained with continued dosing and returned toward baseline after discontinuation.
Main inclusion criteria were a waist circumference of at least 95 cm and a waist-to-hip ratio of at least 0.94 in men (94 cm and 0.88 in women), with fasting glucose below 150 mg/dL. Exclusions included type 1 or type 2 diabetes, a history of malignancy, and hypopituitarism. All participants were on a stable antiretroviral regimen.
Adverse events included injection-site reactions, arthralgias, peripheral edema, and elevated glucose. Participants on tesamorelin had a higher risk of developing diabetes, defined as an HbA1c of 6.5% or higher, than those on placebo. The European Medicines Agency assessment considered the application not approvable when it was withdrawn, citing a modest effect on a biomarker without outcome data, frequent IGF-1 elevations, and anti-drug antibodies.
Subsequent Research and Systematic Reviews
A systematic review and meta-analysis aggregated data from randomized controlled trials in people living with HIV. The analysis confirmed reductions in VAT and improvements in some lipid markers. It also highlighted the need for longer-term data on cardiovascular outcomes and hepatic endpoints.
The IDSA primary care guidance for people with HIV recommends measuring waist circumference annually and lists tesamorelin among promising investigational therapies for HIV-associated fatty liver disease.
| Clinical Parameter | Change at 26 Weeks | Notes |
|---|---|---|
| Visceral adipose tissue area | -14% to -18% (mean, two trials) | Measured by CT |
| Triglycerides | Decreased | Variable magnitude |
| Fasting glucose | HbA1c ≥6.5% in 5% vs 1% on placebo | Monitor glucose and HbA1c |
| Body weight | Minimal change | Not a primary endpoint |
How Tesamorelin Is Used in Practice
Tesamorelin is administered as a daily subcutaneous injection. The peptide is supplied as a lyophilized powder that is reconstituted with the diluent provided. Injection sites rotate to minimize local reactions. Storage requirements depend on the formulation; the current U.S. formulation is stored at room temperature.
Physicians initiate tesamorelin only after confirming eligibility through imaging and metabolic testing. Baseline IGF-1, glucose, and HbA1c are measured. A history of malignancy, pituitary disease, or uncontrolled endocrine disorders may be contraindications.
Monitoring and Adjustment
IGF-1 levels are checked during treatment to assess response and screen for excessive GH stimulation. Elevated IGF-1 may prompt dose interruption or discontinuation. Glucose and HbA1c are re-tested at intervals. Any upward trend requires evaluation and, in some cases, consultation with an endocrinologist.
Imaging is repeated to measure changes in VAT. The physician determines whether the reduction justifies continued use. If VAT does not decrease after six months, continuation is reconsidered.
For patients seeking structured metabolic supervision, tesamorelin may be one component within a broader longevity program that includes biomarker tracking, lifestyle intervention, and physician review.
Contraindications and Precautions
Tesamorelin is contraindicated in patients with active malignancy. Growth hormone can stimulate cell proliferation. A history of cancer requires careful discussion and, often, clearance from an oncologist.
Pituitary tumors or disorders of the hypothalamic-pituitary axis are also contraindications. Disrupted GHRH receptor signaling or existing GH hypersecretion make tesamorelin inappropriate.
Pregnancy is a contraindication because reducing visceral fat offers no benefit during pregnancy and could cause fetal harm; there are no data on use during breastfeeding. Women of childbearing age require counseling and, in some protocols, pregnancy testing.
Diabetes that is not controlled introduces risk. The peptide can raise glucose. Physicians weigh the metabolic benefit of VAT reduction against the risk of worsening glycemic control.
Comparing Tesamorelin to Other Growth Hormone Secretagogues
Tesamorelin is a GHRH analog. Other peptides, such as sermorelin and ipamorelin, also stimulate GH release but through different mechanisms. Sermorelin vs ipamorelin reviews these differences in receptor binding and clinical application.
Sermorelin is another GHRH analog. It lacks the hexenoic acid modification that extends tesamorelin's half-life. Ipamorelin is a ghrelin mimetic that acts on the growth hormone secretagogue receptor. Early animal studies found that it released GH without significant increases in cortisol or prolactin.
No direct head-to-head trials compare these peptides for VAT reduction. Tesamorelin is the only one with FDA approval for a specific metabolic indication. The others are used off-label and remain investigational for most conditions.
GH Replacement Versus Secretagogues
Recombinant human growth hormone provides exogenous GH directly. It bypasses the pituitary. Dosing is more predictable, but the risk of supraphysiologic levels is higher. GH replacement is approved for GH deficiency, not for metabolic fat redistribution.
Secretagogues preserve the body's regulatory feedback. GH is released in pulses. IGF-1 rises more gradually. This may reduce the risk of hyperglycemia and edema, though both can still occur.
The choice depends on the underlying condition, baseline IGF-1, and treatment goals. A physician decides based on imaging, biochemistry, and response to prior interventions.
Adverse Events and Safety Profile
The most common adverse events in tesamorelin trials were injection-site reactions, including erythema, pain, and pruritus. These occurred in a significant portion of participants but rarely led to discontinuation.
Arthralgias and myalgias were reported. These are consistent with known effects of GH on connective tissue and fluid balance. Peripheral edema occurred in some participants, particularly in the first weeks.
Glucose elevations were noted in a subset. The DailyMed prescribing information advises monitoring fasting glucose and HbA1c during treatment. In trials, an HbA1c of 6.5% or higher occurred in 5% of tesamorelin-treated participants versus 1% on placebo.
Rare but Serious Risks
There have been no confirmed cases of new-onset malignancy directly attributable to tesamorelin in clinical trials. However, the theoretical risk exists due to GH's mitogenic effects. Patients with a history of cancer are excluded from trials and, generally, from clinical use.
Eosinophil counts increased in some participants. The clinical significance was unclear.
Hypersensitivity reactions are possible. Any signs of anaphylaxis require immediate discontinuation and supportive care.
| Adverse Event | Frequency in Trials | Management |
|---|---|---|
| Injection-site reactions | Common | Rotation of sites, cold compress |
| Arthralgias | Common | Observation, symptomatic relief |
| Peripheral edema | Occasional | Sodium restriction, monitoring |
| Glucose elevation | Occasional | HbA1c monitoring, possible discontinuation |
Tesamorelin in the Context of Longevity Medicine
Longevity-focused physicians consider interventions that reduce metabolic risk over decades. Visceral adiposity accelerates aging-related pathology. It drives insulin resistance, chronic inflammation, and atherogenesis. Reducing VAT may improve healthspan, though long-term outcome data are limited.
Tesamorelin is one tool within a broader metabolic strategy. It is not a substitute for nutrition, exercise, or management of traditional cardiovascular risk factors. When integrated into a supervised program, it addresses a specific, measurable deficit: excess intra-abdominal fat.
Patients in Bangkok seeking physician-led metabolic care may explore tesamorelin as part of a peptide therapy protocol. Every protocol begins with a consultation, imaging, and biomarker assessment. The physician reviews the data and decides whether the peptide is indicated.
Integration with Other Interventions
Tesamorelin is not typically used alone. It may be combined with dietary modification, resistance training, and management of lipid and glucose abnormalities.
The decision to combine therapies rests on individual biomarkers, treatment goals, and response to initial interventions. Physicians adjust based on re-testing and clinical progress.
For people managing health as a continuous program rather than an annual check, tesamorelin shows why a clear indication matters: its trial data come from one population, and it requires monitoring. This fits the model of physician-led longevity programs built on biomarkers and medical supervision.
Cost and Access Considerations
Tesamorelin is a specialty medication. The branded formulation is expensive. Insurance coverage varies by jurisdiction and indication. In the United States, coverage is typically limited to HIV-associated lipodystrophy.
Compounded versions exist. Quality, purity, and consistency are not assured. Physicians who prescribe compounded peptides should source from licensed pharmacies with third-party testing and sterility certification.
Its registration status in Thailand should be confirmed with the prescribing physician before treatment. Patients should confirm legality and quality before proceeding.
Consultation fees, imaging, and laboratory monitoring add to the total cost. A comprehensive metabolic assessment, including CT imaging for VAT quantification, is necessary before and during treatment.
Realistic Expectations
Tesamorelin reduces visceral fat in a subset of patients who meet trial entry criteria. It does not produce rapid weight loss. It does not eliminate the need for lifestyle modification. Results depend on adherence, baseline VAT, metabolic state, and concurrent interventions.
Some patients see no meaningful reduction in VAT. Others experience adverse effects that require discontinuation. The physician evaluates response and decides whether to continue, adjust, or stop.
Expectations should be set by the data, not by anecdote or marketing. In the FDA trials, mean VAT area fell by 14% to 18% at 26 weeks. Individual results vary.
Who Decides Whether Tesamorelin Is Appropriate
The physician decides. Not the patient. Not a wellness advisor. Not a clinic marketing team. Decision follows examination, review of imaging, and interpretation of metabolic biomarkers.
If VAT is not elevated, tesamorelin is not indicated. If glucose control is poor, the risk may exceed the benefit. If there is a history of malignancy, the peptide is contraindicated.
The physician also decides the frequency of monitoring, the criteria for continuation, and the endpoint at which the intervention is stopped. Some patients use tesamorelin for six months. Others for a year or longer. The duration depends on response and tolerance.
This model of physician-led decision-making defines the approach at private longevity clinics. The focus is not volume. It is precision. Measure, understand, decide. Whether a patient is exploring regenerative treatments or metabolic peptides, the process is the same.
Frequently Asked Questions
What is tesamorelin approved for?
Tesamorelin is FDA-approved for the reduction of excess visceral adipose tissue in adults with HIV-associated lipodystrophy. It is not approved for general obesity, cosmetic fat reduction, or anti-aging.
How long does it take to see results?
In clinical trials, VAT reduction was measured at 26 weeks. Some participants saw changes earlier. Others did not respond. Individual variation is significant. Repeat imaging determines response.
Can tesamorelin cause diabetes?
Tesamorelin can transiently raise fasting glucose and HbA1c. Most cases resolve. Patients with uncontrolled diabetes are at higher risk and may not be candidates. Monitoring is mandatory.
Is tesamorelin the same as growth hormone?
No. Tesamorelin stimulates the body's own release of growth hormone. It does not introduce exogenous GH. The effect is indirect and regulated by the pituitary's feedback mechanisms.
Understanding the science and the boundaries of current evidence helps set realistic expectations.
Tesamorelin reduces visceral adipose tissue in a defined clinical population, supported by controlled trial data and FDA approval. The decision to use it follows imaging, biomarker review, and physician assessment. If you are exploring metabolic interventions as part of a long-term health program, Healthi Life offers physician-led protocols built on diagnostic baselines and continuous supervision in a private setting in Ekkamai, Bangkok.
This page is for information only and is not medical advice. Medical consultation and prescription are available online and on site at Healthi Life, Ekkamai, Bangkok.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
