
B12 Deficiency Symptoms: A Diagnostic Guide

B12 deficiency symptoms include fatigue, neurological changes, memory problems, and anemia. Learn what to test, when to act, and how to decide.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
B12 deficiency symptoms begin with fatigue and progress to numbness, balance problems, memory loss, and mood changes. Severe cases produce macrocytic anemia, peripheral neuropathy, and psychiatric disturbance. The progression is slow; symptoms appear after months or years of declining stores.
The problem is that early b12 deficiency symptoms are vague. Fatigue could be sleep debt. Mild numbness could be posture. Mood changes could be stress. By the time symptoms become obvious, neurological damage may already be measurable.
This guide explains what each symptom indicates, which tests reveal the cause, and when to act.
Neurological Symptoms
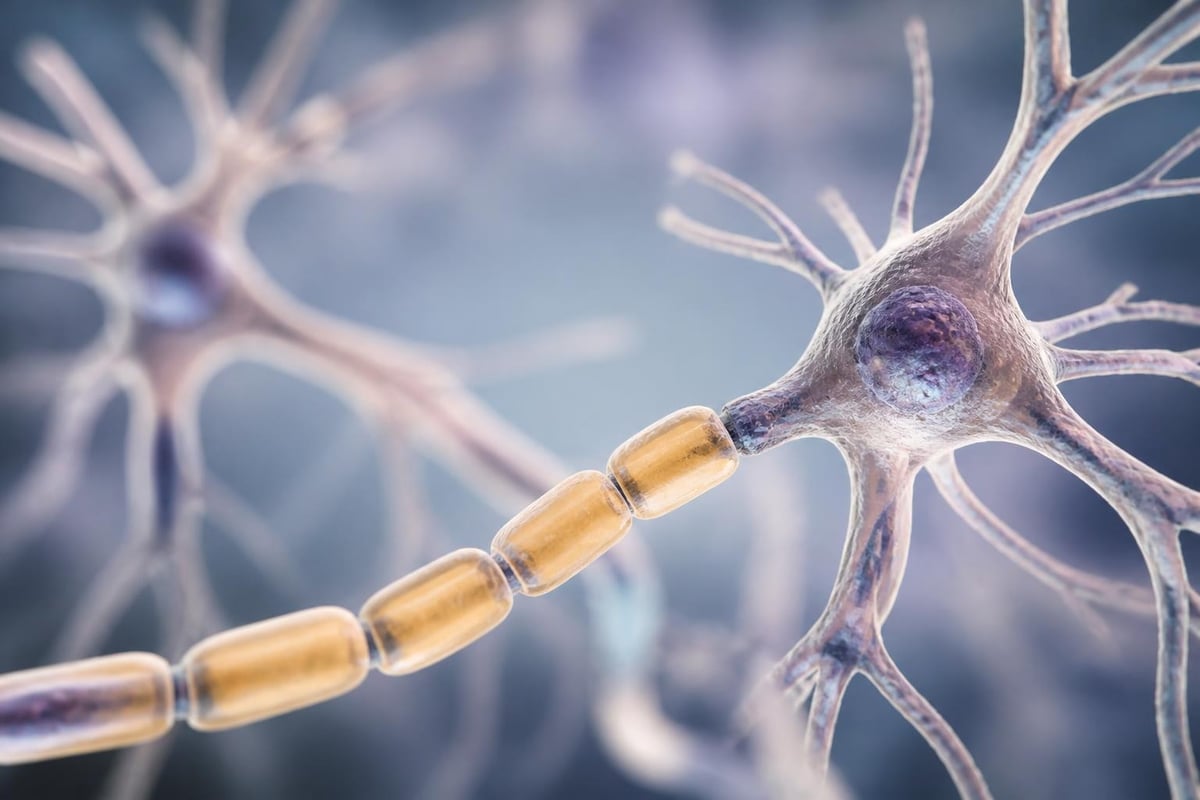
Peripheral neuropathy appears first. Patients report tingling in the hands and feet, numbness, or a sensation of pins and needles. These symptoms reflect damage to the myelin sheath, the insulating layer around nerve fibers. B12 is required for myelin synthesis. Without it, nerve conduction slows. Healthi Life is a physician-led longevity house in Bangkok.
Balance and coordination deteriorate next. Patients may stumble, lose proprioception (the sense of where the body is in space), or have difficulty with fine motor tasks. This is subacute combined degeneration, a specific pattern of spinal cord damage. It affects the dorsal columns and lateral corticospinal tracts.
Clinical evidence from recent peer-reviewed research shows that neurological b12 deficiency symptoms can occur even when blood counts are normal. Hematologic and neurologic manifestations do not always move in parallel. A patient can have profound neuropathy with a hemoglobin level of 130 g/L.
Vision changes occur in advanced cases. Optic neuropathy produces blurred vision, reduced color perception, or central scotomas (blind spots). This is rare but documented.
Cognitive and Psychiatric Symptoms
Memory problems and confusion are common. Patients describe brain fog, difficulty concentrating, or word-finding trouble. These symptoms overlap with early dementia, which is why B12 deficiency must be ruled out in any cognitive workup for adults over 50.
Depression and mood disturbance are well-documented b12 deficiency symptoms. Some patients present with irritability, apathy, or frank depressive episodes. The mechanism is unclear but may involve altered neurotransmitter synthesis or methylation pathway disruption.
Psychosis has been reported in severe cases. Hallucinations, paranoia, and disorganized thinking resolve with B12 replacement. This is uncommon but worth noting in any unexplained psychiatric presentation.
Hematologic Symptoms
Fatigue is the most common symptom. It is also the least specific. Patients describe persistent tiredness that does not improve with sleep. This reflects reduced oxygen-carrying capacity from macrocytic anemia.
Pallor, shortness of breath on exertion, and palpitations follow. These are the classic signs of anemia. Hemoglobin drops slowly over months. The body compensates until it cannot.
Macrocytic anemia means the red blood cells are larger than normal. Mean corpuscular volume (MCV) rises above 100 fL. This is a direct result of impaired DNA synthesis during red blood cell production. Without adequate B12, cells cannot divide properly and remain oversized.
The NHS guidance on B12 and folate deficiency describes these hematologic changes in accessible language and is a useful reference for patient education.
| Hematologic Marker | Normal Range | B12 Deficiency Finding |
|---|---|---|
| Hemoglobin (Hb) | 130–170 g/L (men), 120–150 g/L (women) | Low (anemia present) |
| MCV | 80–100 fL | >100 fL (macrocytic) |
| Serum B12 | >200 pmol/L | <148 pmol/L (deficient) |
| Holotranscobalamin | >35 pmol/L | <35 pmol/L (early marker) |
| Methylmalonic acid | <0.4 µmol/L | Elevated (functional deficiency) |
Pancytopenia (low counts across all blood cell lines) occurs in severe cases. White blood cell and platelet counts drop. This can be mistaken for bone marrow disease or malignancy.
Gastrointestinal and Other Symptoms
Glossitis is inflammation of the tongue. The tongue becomes smooth, red, and painful. Patients may describe a burning sensation or difficulty eating spicy foods. This is a specific sign and should prompt immediate testing.
Mouth ulcers and angular cheilitis (cracks at the corners of the mouth) are less common but recognized b12 deficiency symptoms.
Loss of appetite and unexplained weight loss occur in some patients. The mechanism is unclear but may involve altered gut function or reduced stomach acid production.
Hyperpigmentation of the skin, particularly on the hands and feet, has been reported in patients with darker skin tones. This is uncommon but worth noting for populations in Asia.
Tachycardia (elevated resting heart rate) can occur as the cardiovascular system compensates for reduced oxygen delivery. This is secondary to anemia, not a direct effect of B12 deficiency.
Risk Factors for Adults Over 40 in Asia
Age reduces stomach acid production. Atrophic gastritis, common in older adults, impairs B12 absorption. The vitamin must be cleaved from food proteins by pepsin and acid. Without adequate acid, B12 remains bound and unavailable.
Dietary patterns matter. Adults who follow strict vegetarian or vegan diets without supplementation are at risk. B12 is found only in animal products: meat, fish, eggs, dairy. Plant-based sources are unreliable.
Metformin use is widespread among adults with type 2 diabetes in Asia. Long-term metformin therapy (>3 years) reduces B12 absorption by altering intrinsic factor secretion and ileal uptake. Guidance from the American Family Physician recommends periodic B12 screening for patients on metformin.
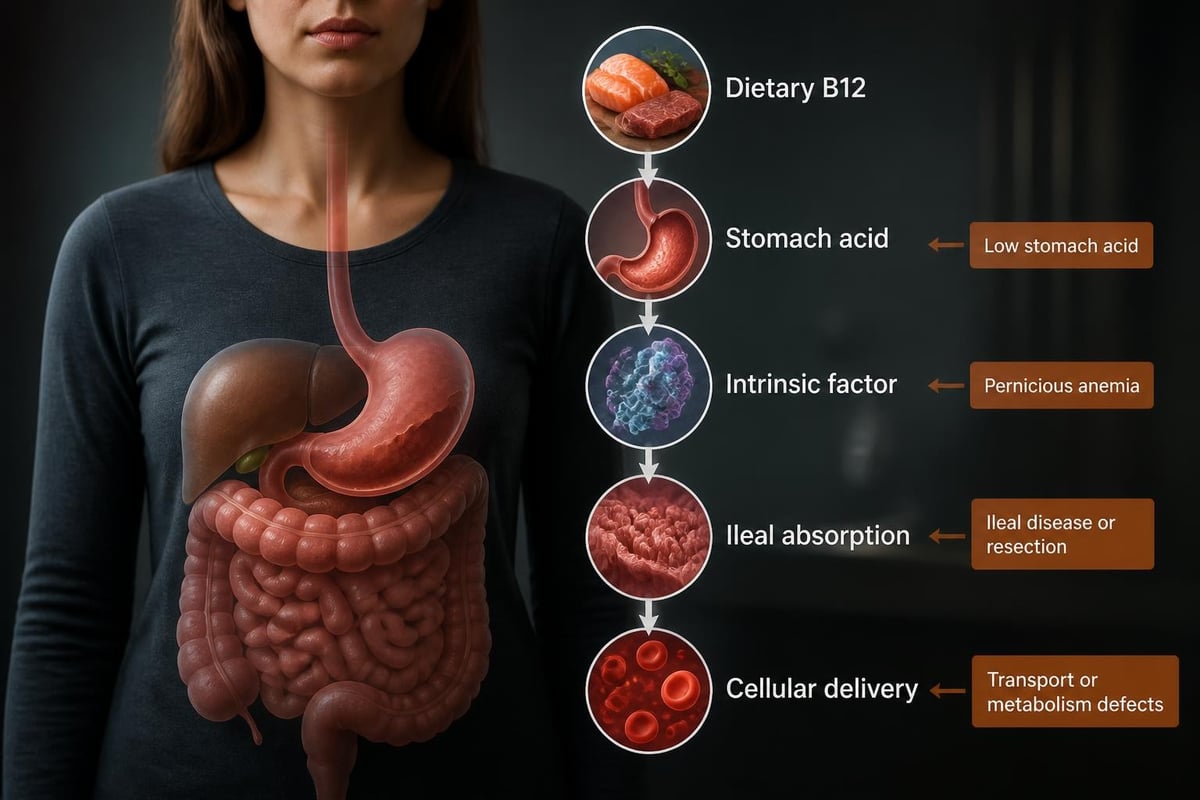
Proton pump inhibitors (PPIs) and H2 blockers suppress acid production. Long-term use (>12 months) increases risk. These medications are commonly prescribed for GERD, gastritis, and ulcers.
Autoimmune conditions, particularly pernicious anemia, occur more frequently in older adults. Antibodies attack intrinsic factor or parietal cells, blocking B12 absorption entirely. This requires lifelong B12 replacement, usually by injection.
Prior gastrectomy or bariatric surgery removes the site of intrinsic factor production. Patients who have undergone gastric bypass or sleeve gastrectomy require lifelong B12 monitoring.
Helicobacter pylori infection, endemic in parts of Asia, causes chronic gastritis and reduces acid production. Eradication improves but does not always normalize B12 status.
Why Symptoms Develop Slowly
The liver stores 2 to 5 mg of B12. Daily losses are approximately 0.1% of total stores. At this rate, it takes 3 to 5 years for a previously healthy adult to develop deficiency after B12 intake stops completely.
This long latency means symptoms appear gradually. Patients often cannot pinpoint when they began. They adapt to worsening fatigue or accept minor neurological changes as normal aging.
Early b12 deficiency symptoms are often dismissed. A patient reports tingling fingers to a physician. The physician suspects carpal tunnel syndrome or cervical radiculopathy. B12 is not measured. Six months later, the tingling has spread, balance is affected, and MCV is 108 fL.
The lesson: b12 deficiency symptoms should prompt testing, not watchful waiting. The neurological damage can become irreversible if left untreated beyond 6 to 12 months.
Some patients present with severe anemia but minimal neurological symptoms. Others have profound neuropathy with normal hemoglobin. This variability reflects differences in how long the deficiency has been present, the rate of decline, and individual susceptibility.
Diagnosis and Testing
Serum B12 is the first test. A level below 148 pmol/L confirms deficiency in most labs. Levels between 148 and 221 pmol/L are considered borderline and require further investigation.
Holotranscobalamin (holoTC) is a more sensitive early marker. It measures the active fraction of B12 bound to transcobalamin II. Low holoTC indicates early depletion before total B12 falls.
Methylmalonic acid (MMA) and homocysteine rise when B12 function is impaired. Elevated MMA (>0.4 µmol/L) confirms functional deficiency even when serum B12 is borderline. Homocysteine is less specific because it also rises in folate deficiency and renal impairment.
Complete blood count (CBC) reveals macrocytosis and anemia if present. Peripheral blood smear may show hypersegmented neutrophils, a specific finding.
Intrinsic factor antibodies and parietal cell antibodies are tested when pernicious anemia is suspected. Positive antibodies confirm the diagnosis but negative results do not rule it out.
The Foundation health check-up in Bangkok includes a comprehensive biomarker panel that measures serum B12, MCV, and other markers of nutritional status. Results are reviewed one-to-one with a physician, who interprets the findings in the context of symptoms, medical history, and risk factors. The Foundation tier is priced at THB 10,500, published and all-inclusive, with no separate lab fees.
Treatment Options
Oral B12 (1000 to 2000 mcg daily) is effective for most patients who can absorb it. This includes dietary deficiency and mild malabsorption. High-dose oral therapy saturates passive absorption pathways, bypassing the need for intrinsic factor.
Intramuscular (IM) B12 is required for pernicious anemia and severe malabsorption. The standard protocol is 1000 mcg daily for one week, then weekly for four weeks, then monthly for life. Neurological symptoms require more aggressive dosing.
Sublingual and nasal formulations exist but are less well-studied. Response should be monitored by repeat testing.
Improvement begins within days to weeks for hematologic symptoms. Hemoglobin rises, MCV normalizes, and fatigue improves. Neurological recovery is slower and may be incomplete if damage is longstanding.
Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription.

Monitoring and Follow-Up
Repeat testing at 8 to 12 weeks confirms response. Hemoglobin, MCV, and B12 levels should normalize. If they do not, consider compliance, malabsorption, or an alternative diagnosis.
Long-term monitoring depends on the cause. Dietary deficiency requires periodic checks to ensure adherence to supplementation. Pernicious anemia requires lifelong IM B12 and annual follow-up.
Patients on metformin, PPIs, or other medications that impair absorption should be screened annually. Longevity medicine programs built on up to 300 biomarkers include scheduled re-testing and protocol adjustment under continuous physician supervision. This approach identifies deficiency before symptoms appear.
Neurological symptoms may continue to improve for 6 to 12 months after B12 normalization. Residual deficits, particularly in balance and proprioception, may persist if treatment was delayed.
Patients with similar symptoms, such as low ferritin symptoms, benefit from a diagnostic approach that measures multiple biomarkers simultaneously rather than chasing individual symptoms.
When to Get Tested
Adults over 40 should measure B12 during routine health assessments, particularly if they take metformin, PPIs, or follow a vegetarian diet. Annual testing is reasonable in these groups.
Test immediately if you experience:
- Persistent fatigue unresponsive to sleep or lifestyle changes
- Tingling, numbness, or burning in the hands or feet
- Balance problems, coordination difficulty, or unexplained falls
- Memory loss, confusion, or difficulty concentrating
- Smooth, red, painful tongue or mouth ulcers
- Unexplained anemia found on routine blood work
The test is serum B12, ideally with MCV and a complete blood count. If serum B12 is borderline, request methylmalonic acid.
Testing is available through primary care physicians, hematology clinics, and longevity medicine programs. Results should be reviewed by a physician who can interpret them in context and recommend next steps.
Frequently Asked Questions
Can B12 deficiency cause permanent damage?
Yes. Neurological damage that persists for more than 6 to 12 months may become irreversible. Early diagnosis and treatment prevent this outcome. Hematologic abnormalities reverse completely with replacement.
Pernicious anemia, gastrectomy, and severe malabsorption require intramuscular B12. A physician decides after reviewing test results and medical history.
How long does it take for symptoms to improve?
Fatigue and anemia improve within 4 to 8 weeks. Neurological symptoms improve more slowly, over 3 to 12 months. Some residual deficits may persist if treatment is delayed.
Can B12 deficiency be prevented?
Yes. Adults on vegetarian or vegan diets should take 1000 mcg B12 daily or eat fortified foods. Patients on metformin or PPIs should be screened annually. Those with a family history of pernicious anemia should request periodic testing.
Is B12 testing included in standard blood panels?
Not always. Some panels include it; others do not. Request it specifically if you have risk factors or symptoms. Comprehensive panels that measure B12, MMA, and folate provide a complete picture.
B12 deficiency symptoms progress slowly but produce measurable neurological, hematologic, and cognitive changes. Testing reveals the deficit before permanent damage occurs. Interpretation requires a physician who understands which biomarkers matter and when to act. Healthi Life in Ekkamai, Bangkok measures up to 300 biomarkers, reviews results one-to-one, and builds treatment protocols based on evidence, not assumptions.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
