
Insulin Resistance Symptoms: What You Need to Know

Learn the key insulin resistance symptoms, how they develop, and which biomarkers reveal cellular dysfunction before clinical disease appears.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. GLP-1 medication (semaglutide — Ozempic, Wegovy; tirzepatide — Mounjaro) is a prescription medicine, dispensed and administered only after assessment by a licensed physician. This page is medical information, not an advertisement or an offer of treatment. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
Insulin resistance symptoms appear when cells stop responding normally to insulin, forcing the pancreas to produce more of the hormone to maintain blood glucose control. The cellular dysfunction precedes clinical diabetes by years, often by a decade or longer. According to the NIDDK, people with insulin resistance and prediabetes usually have no symptoms; when symptoms appear, they are nonspecific, such as fatigue, abdominal weight gain and difficulty concentrating. A physician diagnoses insulin resistance through biomarker panels that include fasting insulin, glucose, HbA1c, and lipid profiles, not through symptoms alone.
How Insulin Resistance Develops
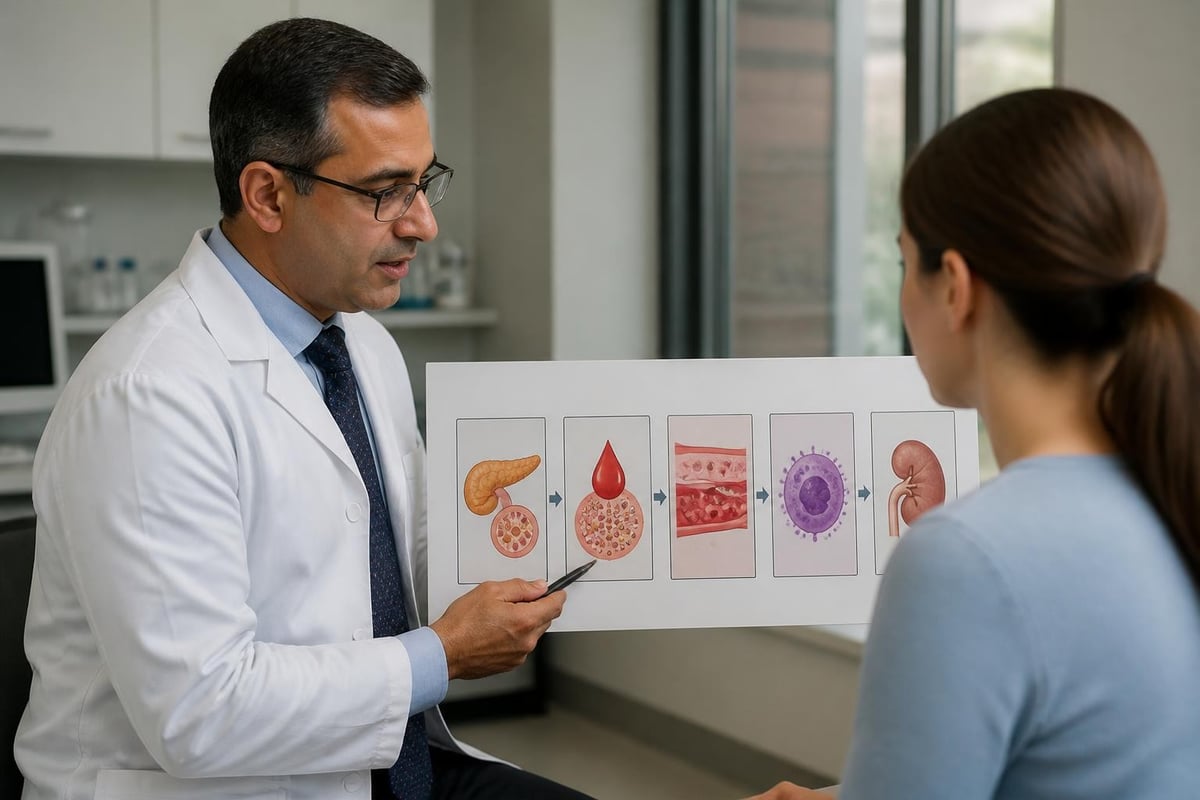
Insulin binds to receptors on muscle, fat, and liver cells. The receptor triggers a cascade that moves glucose transporters to the cell surface. Glucose enters. Energy is stored or used. This guide is published by the Healthi Life longevity clinic in Bangkok.
When cells stop responding to insulin's signal, the pancreas compensates by releasing more. Blood insulin rises while blood glucose remains stable. This is early-stage insulin resistance. The patient feels nothing yet.
Over months to years, the pancreas cannot keep pace. Glucose begins to rise after meals, then while fasting. HbA1c creeps upward. Triglycerides increase. HDL cholesterol falls. Inflammation markers appear. The patient now experiences symptoms.
Key progression stages:
- Cellular resistance begins, no symptoms, normal glucose
- Fasting insulin rises (compensatory hyperinsulinemia)
- Post-meal glucose spikes above 140 mg/dL
- Fasting glucose reaches 100-125 mg/dL (prediabetes range)
- HbA1c crosses 5.7% threshold
The exact mechanism varies. Excess visceral fat releases inflammatory cytokines that block insulin signaling. Saturated fat accumulation in liver and muscle cells disrupts the insulin receptor pathway. Mitochondrial dysfunction reduces cellular energy capacity. The gut microbiome composition shifts, altering metabolism and inflammation.

Early Insulin Resistance Symptoms
Fatigue is often reported, although it is nonspecific. Cells cannot efficiently take up glucose for energy. The body runs on elevated insulin, which promotes fat storage and inhibits fat burning. Mental energy drops mid-afternoon. Physical tasks feel harder.
Increased hunger follows. High insulin drives hunger signals even when caloric intake is adequate. Cravings focus on carbohydrates and sweets. The body seeks quick glucose to compensate for poor cellular uptake.
Common early symptoms:
- Persistent fatigue, especially after meals
- Difficulty maintaining focus or mental clarity
- Increased hunger and carbohydrate cravings
- Gradual weight gain, particularly around the waist
- Darkened skin patches on neck, armpits, or groin (acanthosis nigricans)
Sleep quality often deteriorates. Heart rate variability drops. The autonomic nervous system tilts toward sympathetic dominance. Patients wake unrefreshed.
Skin changes provide visible evidence. Acanthosis nigricans presents as dark, velvety patches in body folds. The high insulin stimulates skin cell growth. Skin tags may appear.
Women may notice irregular menstrual cycles. Insulin resistance is recognized as a pathophysiological factor in polycystic ovary syndrome, affecting ovulation and hormone balance. Excess insulin raises testosterone production in the ovaries.
Metabolic and Physical Symptoms
Abdominal weight accumulates despite stable caloric intake. Insulin resistance shifts metabolism toward fat storage. Visceral fat grows around internal organs. Waist circumference increases. The fat itself worsens insulin resistance, creating a self-reinforcing cycle.
Blood pressure rises in many patients. Insulin affects sodium retention and vascular tone. High blood pressure, a large waist, high triglycerides, low HDL cholesterol and high fasting glucose are the risk factors used to diagnose metabolic syndrome, according to the NHLBI; waist thresholds may differ by ethnicity.
| Metabolic Parameter | Normal Range | Insulin Resistance Pattern |
|---|---|---|
| Fasting insulin | No standardized cutoff | Interpreted by a physician with glucose and lipids |
| Fasting glucose | <100 mg/dL | 100-125 mg/dL |
| HbA1c | <5.7% | 5.7-6.4% |
| Triglycerides | <150 mg/dL | >150 mg/dL |
| HDL cholesterol | >40 mg/dL (men), >50 mg/dL (women) | Below threshold |
| Waist circumference | <102 cm (men), <88 cm (women) | Above threshold |
Inflammation becomes measurable. High-sensitivity C-reactive protein rises. Insulin resistance and inflammation share bidirectional causation. Fat tissue releases inflammatory molecules. Inflammation blocks insulin signaling. The cycle perpetuates.
Non-alcoholic fatty liver disease develops when insulin resistance affects the liver. Fat accumulates in hepatocytes. Liver enzymes elevate. The condition progresses silently until imaging or biomarker testing reveals it.
Cognitive and Neurological Symptoms
Brain fog describes the subjective experience of reduced mental clarity. Patients report difficulty with word retrieval, slower processing speed, and impaired working memory. The brain depends on glucose, yet insulin resistance affects neuronal glucose uptake and utilization.
Concentration lapses occur throughout the day. Tasks requiring sustained attention become exhausting. Multitasking capacity drops. The symptoms worsen after high-carbohydrate meals when glucose and insulin spike then crash.
Neurological manifestations:
- Reduced mental clarity and processing speed
- Difficulty maintaining concentration
- Impaired short-term memory
- Increased mental fatigue
- Mood changes, including anxiety or depression
Research links insulin resistance to neurodegenerative risk. The brain becomes less sensitive to insulin's effects on neuronal signaling, synaptic plasticity, and amyloid clearance. In a pooled analysis of 2.3 million people, type 2 diabetes was associated with about a 60% higher risk of dementia.
Mood regulation suffers. Insulin affects neurotransmitter systems. Chronic inflammation reaches the brain. Patients describe increased irritability, anxiety, or low mood that does not match life circumstances.
Cardiovascular and Vascular Symptoms
Small fiber neuropathy may appear before diabetes diagnosis. Patients describe tingling, numbness, or burning sensations in hands and feet. High glucose and insulin levels damage small nerve fibers. The symptoms start distally and progress proximally.
Vascular health declines. Endothelial dysfunction develops when high insulin and glucose impair nitric oxide production. Blood vessels lose elasticity. Atherosclerosis accelerates. The process is silent until advanced.
Exercise capacity decreases. Insulin resistance impairs muscle glucose uptake during activity. Lactate accumulates faster. Recovery takes longer. Athletic performance drops even when training volume remains constant.
Cardiovascular indicators:
- Elevated blood pressure, particularly systolic
- Increased resting heart rate
- Reduced exercise tolerance
- Prolonged recovery after exertion
- Erectile dysfunction in men (vascular and hormonal)
Erectile dysfunction appears years before cardiovascular events in men with insulin resistance. The same endothelial dysfunction that reduces penile blood flow affects coronary and cerebral vessels. The symptom serves as an early warning.
Diagnostic Biomarkers
Symptoms prompt investigation, but biomarkers quantify the dysfunction. A physician orders specific tests based on clinical presentation and family history.
Fasting insulin can rise before fasting glucose in early stages. However, there is no universally accepted insulin cutoff, and the NIDDK notes that the test for insulin resistance is primarily used in research, so a physician interprets fasting insulin alongside glucose, HbA1c and lipids.
| Test | Purpose | Threshold for Concern |
|---|---|---|
| Fasting insulin | Measures compensatory hyperinsulinemia | No universal cutoff |
| Fasting glucose | Detects impaired glucose regulation | >100 mg/dL |
| HbA1c | Reflects 3-month average glucose | >5.7% |
| Oral glucose tolerance test | Reveals post-meal glucose handling | >140 mg/dL at 2 hours |
| HOMA-IR | Calculates insulin resistance index | No universal cutoff |
| Triglyceride/HDL ratio | Indicates metabolic dysfunction | No universal cutoff |
HOMA-IR combines fasting glucose and insulin into a single metric: (glucose × insulin) / 405 when using conventional units. The calculation estimates insulin resistance severity. Cutoffs vary between populations and laboratories, so there is no single universal threshold.
Advanced lipid panels reveal small, dense LDL particles. Insulin resistance shifts lipoprotein metabolism toward atherogenic patterns. Apolipoprotein B rises. Lipoprotein(a) may be measured as part of comprehensive cardiovascular risk assessment.
Advanced check-up protocols include baseline biomarker panels reviewed with a physician who interprets results in context. The consultation translates numbers into actionable decisions about intervention timing and approach.
Who Develops Insulin Resistance
Risk accumulates through genetics, lifestyle, and environment. A family history of type 2 diabetes increases risk. Certain ethnic groups show higher prevalence, including South Asian, East Asian, and Hispanic populations.
Age affects insulin sensitivity. Muscle mass declines with age, especially without resistance training. Physical inactivity reduces glucose disposal capacity. Mitochondrial function decreases. Insulin resistance prevalence rises with each decade.
High-risk groups:
- Family history of type 2 diabetes or metabolic syndrome
- Sedentary lifestyle with minimal physical activity
- Overweight or obese, particularly with visceral adiposity
- History of gestational diabetes
- Polycystic ovary syndrome diagnosis
- Sleep disorders, including obstructive sleep apnea
Gestational diabetes identifies women with insulin resistance that pregnancy hormones unmask. The condition usually resolves after delivery, but about half of women with gestational diabetes go on to develop type 2 diabetes.
Sleep deprivation worsens insulin sensitivity. Even a few nights of poor sleep increase insulin resistance measurably in experimental studies. In a meta-analysis of prospective cohorts, habitually short sleep was associated with a 28% higher risk of type 2 diabetes.
Medications contribute in some cases. Corticosteroids, atypical antipsychotics, and certain antiretrovirals impair insulin signaling. The physician weighs therapeutic benefit against metabolic risk when prescribing.

Measuring Insulin Resistance Symptoms Through Testing
Symptoms correlate imperfectly with insulin resistance severity. Some patients with marked biomarker abnormalities report minimal symptoms. Others experience significant fatigue and cognitive changes with only modest laboratory findings.
A physician reviews symptoms alongside objective data. The combination guides decision-making. Isolated symptoms without biomarker evidence may indicate other conditions. Normal biomarkers with symptoms prompt investigation of thyroid function, cortisol patterns, or nutrient deficiencies.
Testing frequency depends on risk level and baseline results. Annual screening suffices for low-risk individuals with normal results. High-risk patients benefit from quarterly monitoring during intervention. Biomarker improvement confirms protocol effectiveness before symptoms resolve.
Testing timeline:
- Baseline comprehensive metabolic panel
- Three-month follow-up after intervention starts
- Six-month assessment with expanded biomarkers
- Annual monitoring once stable
Continuous glucose monitors provide detailed data on glucose patterns throughout the day. The devices measure interstitial glucose every few minutes. Post-meal spikes, overnight trends, and variability become visible. The information guides dietary and timing interventions.
The technology suits patients who want precise feedback on how specific foods and activities affect their metabolism. A physician interprets the data, identifying patterns that predict progression or improvement.
Intervention Approaches
Lifestyle modification forms the foundation. In the Diabetes Prevention Program, a lifestyle program targeting at least 7% weight loss and 150 minutes of weekly activity reduced the incidence of type 2 diabetes by 58% in high-risk adults. The loss must come from fat mass, particularly visceral fat, not muscle mass.
Resistance training builds muscle, which serves as the primary glucose disposal site. Regular resistance sessions built on compound movements improve insulin sensitivity.
Dietary approaches vary. Low-carbohydrate patterns reduce insulin demand. Time-restricted eating improves metabolic flexibility. Adequate protein intake, set with a physician or dietitian, helps preserve muscle during weight loss. No single diet suits all patients.
Evidence-based interventions:
- Progressive resistance training on a regular weekly schedule
- Aerobic exercise accumulating 150+ minutes weekly
- Weight loss targeting visceral fat reduction
- Carbohydrate intake matched to activity level
- Sleep optimization to 7-9 hours nightly
- Stress management to lower cortisol exposure
Pharmaceutical options exist when lifestyle intervention proves insufficient. Metformin improves hepatic insulin sensitivity and reduces glucose production. GLP-1 receptor agonists enhance insulin secretion and promote weight loss. A physician prescribes based on specific biomarker patterns and clinical context.
Some patients pursue longevity programs built on comprehensive biomarker testing repeated at scheduled intervals. The approach allows protocol adjustment based on measurable changes rather than symptoms alone. The physician supervises throughout.
Frequently Asked Questions
What is the earliest sign of insulin resistance?
Elevated fasting insulin can appear years before glucose rises or symptoms develop. A physician detects it through biomarker testing, not clinical examination. Many patients have no symptoms when insulin first becomes abnormal.
Can insulin resistance be reversed?
Yes, through weight loss, exercise, and dietary intervention in most cases. Biomarkers improve within months when patients lose visceral fat and increase muscle mass. Complete normalization occurs in some patients. Others require ongoing management even with lifestyle optimization.
How accurate are symptoms for diagnosing insulin resistance?
Symptoms alone cannot diagnose insulin resistance. Fatigue, weight gain, and concentration difficulties occur in many conditions. A physician uses biomarker panels to confirm the diagnosis and quantify severity. Symptoms guide the decision to test but do not replace testing.
Which biomarker matters most?
Fasting insulin reveals insulin resistance earliest. Glucose and HbA1c lag behind insulin elevation by years. A physician reviews the full panel, not a single marker, because metabolic dysfunction affects multiple systems. The pattern of abnormalities guides intervention.
Insulin resistance symptoms develop gradually as cellular dysfunction progresses through measurable biomarker changes toward clinical disease. Early detection through testing allows intervention before irreversible complications appear.
Healthi Life builds longevity protocols on comprehensive biomarker assessment reviewed one-to-one with a physician. Testing identifies insulin resistance at the earliest stage. The physician translates results into a specific protocol adjusted through scheduled re-testing. Located in Ekkamai, Bangkok, the private house serves residents and international visitors who want continuous medical supervision rather than annual check-ups.
This page is for information only and is not medical advice. Medical consultation and prescription are available online and on site at Healthi Life, Ekkamai, Bangkok.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
