
Triglycerides Normal Range: Values, Testing, and Risks

Triglycerides normal range is under 150 mg/dL. Learn the reference values, testing protocols, and what elevated levels mean for adults 40+.
This page is for general information and does not constitute medical advice, diagnosis, or treatment. Results vary between individuals. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. Prices are published for transparency, not as an offer to supply. Always consult a qualified physician about your condition. See our full medical disclaimer.
The triglycerides normal range is under 150 mg/dL when fasting. This threshold separates desirable values from borderline-high levels. A fasting test measures these lipid molecules after eight to twelve hours without food, ensuring the result reflects stored fat rather than recent intake.
What Triglycerides Are and Why They Matter
Triglycerides are the primary storage form of fat in the human body. After a meal, the digestive system converts calories not immediately needed into triglycerides, which circulate in the bloodstream or move into adipose tissue. Between meals, hormones signal the release of these molecules to supply energy. Healthi Life is a physician-led longevity house in Bangkok.
Elevated triglycerides contribute to residual atherosclerotic cardiovascular disease (ASCVD) risk, even when LDL cholesterol is controlled. Remnant lipoproteins, which carry triglycerides, penetrate the arterial wall and promote plaque formation. The mechanisms underlying hypertriglyceridaemia and residual ASCVD risk are an active area of cardiovascular research.
Very high levels above 500 mg/dL increase the risk of acute pancreatitis, a medical emergency. The pancreas becomes inflamed when excess triglycerides overwhelm its enzymatic capacity.
Reference Values and Clinical Categories
The table below presents the triglycerides normal range and clinical thresholds used in laboratory interpretation.
| Category | Triglyceride Level (mg/dL) | Clinical Significance |
|---|---|---|
| Desirable | <150 | Optimal cardiovascular risk profile |
| Borderline high | 150–199 | Intervention warranted if other risk factors present |
| High | 200–499 | Lifestyle modification required; medication considered |
| Very high | ≥500 | Acute pancreatitis risk; immediate pharmacologic therapy |
These cutoffs align with the American Diabetes Association's 2024 cardiovascular disease and risk management guidelines, which address both moderate elevations and severe hypertriglyceridaemia in people with diabetes.
The Endocrine Society published a detailed clinical practice guideline on hypertriglyceridemia evaluation and treatment, outlining diagnostic pathways and secondary causes such as hypothyroidism, nephrotic syndrome, and alcohol consumption.
How the Test Is Performed
A fasting lipid panel measures total cholesterol, LDL cholesterol, HDL cholesterol, and triglycerides. The patient abstains from all food and caloric beverages for eight to twelve hours before blood is drawn, typically in the morning. Water is permitted.
Some laboratories now offer non-fasting lipid panels, but fasting remains the standard for triglyceride measurement because postprandial values can exceed 200 mg/dL even in healthy individuals. The CDC laboratory method document for NHANES triglyceride testing details analytical measurement ranges and standardization protocols used in population surveillance.
Blood is collected in a tube containing an anticoagulant, centrifuged to separate serum or plasma, and analyzed using enzymatic colorimetric assays. Results are typically available within 24 to 48 hours.
Factors That Affect Triglyceride Levels
Diet exerts the most immediate influence. Simple carbohydrates, fructose, and alcohol raise triglycerides more sharply than dietary fat. A single high-sugar meal can elevate levels by 30 to 50 mg/dL within hours.
Common dietary contributors:
- Refined grains and white rice
- Sugar-sweetened beverages and fruit juice
- Pastries and desserts
- Alcohol, particularly beer and spirits in excess
Physical inactivity also drives hypertriglyceridaemia. Skeletal muscle is the primary site of triglyceride clearance during and after exercise. A sedentary lifestyle reduces lipoprotein lipase activity, the enzyme responsible for breaking down circulating triglycerides. Zone 2 training, a moderate-intensity cardiovascular exercise protocol, is one of the most effective non-pharmacologic interventions for improving lipid metabolism.
Medical conditions associated with elevated triglycerides:
- Type 2 diabetes and insulin resistance
- Metabolic syndrome
- Hypothyroidism
- Chronic kidney disease
- Polycystic ovary syndrome
Certain medications raise triglycerides as a side effect, including corticosteroids, beta-blockers, thiazide diuretics, and some antiretroviral drugs used in HIV treatment. Estrogen therapy and tamoxifen can also increase levels.
Genetic forms of hypertriglyceridaemia exist. Familial chylomicronemia syndrome, caused by mutations in genes encoding lipoprotein lipase or its cofactors, results in triglyceride levels exceeding 1,000 mg/dL even with dietary restriction.

Interpretation in Adults Over 40
The triglycerides normal range does not change with age, but the clinical context does. Metabolic efficiency declines after 40. Lean muscle mass decreases, visceral adiposity increases, and insulin sensitivity worsens. These shifts raise baseline triglyceride levels even without dietary changes.
A 45-year-old with triglycerides at 170 mg/dL may have no other cardiovascular risk factors and require only lifestyle modification. The same value in a 55-year-old with hypertension, prediabetes, and a family history of coronary artery disease warrants pharmacologic intervention.
Triglycerides should be interpreted alongside other biomarkers. The triglyceride-to-HDL cholesterol ratio, calculated by dividing triglycerides by HDL cholesterol (both in mg/dL), serves as a surrogate marker for insulin resistance. A ratio above 3.0 suggests metabolic dysfunction. A ratio above 5.0 is strongly associated with cardiovascular events.
ApoB, which quantifies all atherogenic lipoprotein particles, provides additional context. An individual with triglycerides at 180 mg/dL and ApoB at 120 mg/dL carries more cardiovascular risk than someone with the same triglyceride level but ApoB at 80 mg/dL.
Women experience a sharp rise in triglycerides during menopause as estrogen's cardioprotective effects wane. This change often coincides with menopause weight gain and redistribution of fat to the abdominal region. Men typically see gradual increases throughout middle age, particularly if testosterone levels decline.
What to Do When Levels Are Elevated
The physician reviews the full lipid panel, medical history, and concurrent risk factors before recommending a course of action. Borderline-high triglycerides (150–199 mg/dL) respond well to dietary changes and exercise in most cases.
First-line interventions for borderline-high triglycerides:
- Eliminate refined carbohydrates and sugar-sweetened beverages
- Limit alcohol to no more than one drink per day
- Increase omega-3 fatty acid intake from fatty fish or supplements
- Establish a consistent exercise routine targeting 150 minutes per week
High triglycerides (200–499 mg/dL) may require medication if lifestyle changes are insufficient after three to six months. Fibrates, niacin, and high-dose omega-3 fatty acids (2–4 grams daily of EPA and DHA) are the primary pharmacologic options. Statins lower triglycerides modestly as a secondary effect of LDL reduction.
Very high triglycerides (≥500 mg/dL) demand immediate treatment to prevent pancreatitis. Hospitalization may be necessary if levels exceed 1,000 mg/dL. Intravenous insulin, restriction of all dietary fat, and fibrate therapy are initiated simultaneously.
The Foundation health check-up in Bangkok at Healthi Life includes a fasting lipid panel, comprehensive metabolic panel, and one-to-one review with a physician. The test is part of a THB 10,500 published and all-inclusive package with no separate lab fees. Results are interpreted in the context of individual risk factors and turned into a written plan.
Secondary Causes and Underlying Conditions
An unexplained elevation in triglycerides warrants investigation for secondary causes. Thyroid-stimulating hormone (TSH) rules out hypothyroidism, a common and treatable contributor. Hemoglobin A1c and fasting glucose assess for diabetes and prediabetes.
Kidney function tests identify nephrotic syndrome or chronic kidney disease, both of which impair triglyceride clearance. Liver enzymes screen for non-alcoholic fatty liver disease (NAFLD), which frequently coexists with hypertriglyceridaemia as part of metabolic syndrome.
Medication history is reviewed. If a drug is identified as the cause, the physician weighs the benefit of continuing it against the cardiovascular risk posed by elevated triglycerides. Alternative medications may be available.
A family history of premature cardiovascular disease or very high triglycerides in multiple relatives suggests genetic dyslipidaemia. Genetic testing is considered in cases of severe hypertriglyceridaemia without obvious secondary causes.
Lifestyle factors are reassessed. Alcohol consumption is quantified. Dietary intake of simple carbohydrates, fructose-containing foods, and saturated fats is documented. Physical activity level and body composition are evaluated, as sarcopenia and reduced muscle mass diminish the body's capacity to clear triglycerides efficiently.
Tea, Polyphenols, and Lipid Metabolism
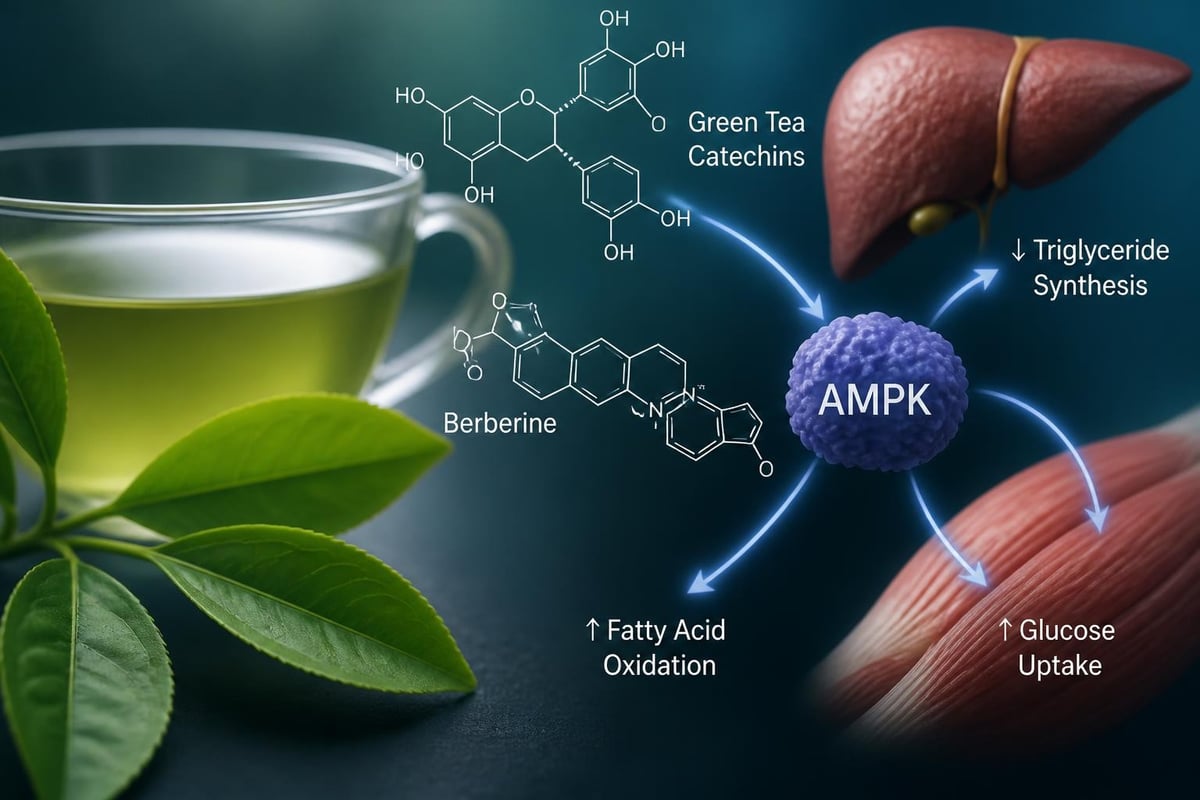
Certain plant compounds influence lipid metabolism through multiple pathways. Catechins, a class of polyphenols abundant in green tea, enhance hepatic lipid oxidation and reduce triglyceride synthesis. Epigallocatechin gallate (EGCG), the most studied catechin, activates AMP-activated protein kinase (AMPK), a master regulator of cellular energy metabolism.
Clinical trials have shown that daily consumption of green tea or green tea extract can lower triglycerides by 10 to 20 mg/dL in individuals with borderline-high levels. The effect is modest but consistent across studies. Oolong and black teas contain lower concentrations of catechins due to oxidation during processing but still provide measurable benefit.
Berberine, a compound found in several plants used in traditional medicine, lowers triglycerides by 30 to 50 mg/dL through inhibition of mitochondrial complex I and subsequent AMPK activation. It also improves insulin sensitivity and glucose uptake in muscle tissue. Every medicine and peptide listed here is dispensed only after a medical consultation at Healthi Life and on a physician's prescription.
Brewing parameters matter: water temperature between 75 and 85°C for green tea and steeping time of two to three minutes maximize catechin extraction without excessive bitterness from tannins.
Monitoring and Long-Term Management
Triglyceride levels fluctuate. A single elevated value does not establish a diagnosis of hypertriglyceridaemia. The test is repeated after two to three weeks, ensuring fasting conditions are identical. If both results exceed 150 mg/dL, intervention begins.
Follow-up testing occurs at intervals determined by the initial severity and the chosen intervention. Lifestyle changes alone warrant re-testing after three months. Medication requires a lipid panel six weeks after initiation to confirm therapeutic effect and check for adverse events such as liver enzyme elevation with fibrates or myopathy with statin-fibrate combinations.
Once triglycerides normalize, annual monitoring suffices for most individuals. Those with metabolic syndrome, diabetes, or persistent borderline-high values despite treatment are tested every six months. The physician may adjust medication doses or add a second agent based on response.
Advanced lipid testing, including apolipoprotein B, lipoprotein(a), and LDL particle number, provides a more detailed cardiovascular risk assessment. These tests are not routine but are considered in patients with strong family histories, premature coronary artery disease, or discordance between calculated and measured LDL cholesterol.
Integration with other biomarkers is essential. Hemoglobin A1c tracks glycemic control. High-sensitivity C-reactive protein (hs-CRP) measures inflammation. Coronary artery calcium scoring quantifies atherosclerotic burden. Together, these data points guide decisions about intensifying therapy.
Longevity medicine programs at Healthi Life build on up to 300 biomarkers, with triglycerides as one component of a comprehensive metabolic profile. Scheduled re-testing and continuous physician supervision ensure that interventions are adjusted as physiology changes over months and years.
Frequently Asked Questions
What is considered a normal triglyceride level after eating?
There is no established triglycerides normal range for postprandial testing. Non-fasting triglycerides can exceed 200 mg/dL even in healthy individuals after a carbohydrate-rich meal. Clinical decisions are based on fasting values obtained after eight to twelve hours without food.
Can triglycerides be too low?
Triglyceride levels below 50 mg/dL are uncommon but not inherently harmful. Severe malnutrition, malabsorption disorders, and hyperthyroidism can cause very low values. A single low reading without symptoms requires no intervention, but persistently low levels warrant evaluation for an underlying condition.
How long does it take to lower triglycerides naturally?
Dietary changes and exercise can reduce triglycerides by 20 to 30 percent within four to six weeks. The most rapid improvements occur in individuals with very high baseline levels. Eliminating alcohol and refined carbohydrates produces measurable change within two weeks.
Do triglycerides affect cholesterol levels?
Triglycerides and cholesterol are separate lipid molecules, but their metabolism is interconnected. High triglycerides often occur alongside low HDL cholesterol and small, dense LDL particles, a pattern known as atherogenic dyslipidemia. Lowering triglycerides can modestly increase HDL cholesterol.
Is a triglyceride level of 160 mg/dL dangerous?
A level of 160 mg/dL falls into the borderline-high category (150–199 mg/dL). It is not immediately dangerous but indicates increased cardiovascular risk, particularly if other risk factors are present. Lifestyle modification is the first step. The physician decides whether medication is necessary based on the full clinical picture.
When to Get Tested
Adults over 40 should have a fasting lipid panel, which includes triglycerides, every one to three years as part of routine cardiovascular risk assessment. More frequent testing is indicated for individuals with diabetes, metabolic syndrome, obesity, or a family history of premature heart disease.
The test is called a lipid panel or lipid profile. It is performed in the morning after an overnight fast. Water is permitted, but coffee, tea, and any food or caloric beverages must be avoided for at least eight hours before blood is drawn.
Anyone experiencing unexplained weight gain, abdominal discomfort after meals, or new-onset fatigue should discuss triglyceride testing with a physician. These symptoms are non-specific but can accompany metabolic dysfunction.
Individuals starting medications known to raise triglycerides, such as corticosteroids or antiretrovirals, require baseline and periodic monitoring. The physician establishes a testing schedule based on the drug, dose, and individual risk factors.
The triglycerides normal range is a single data point within a broader metabolic assessment. Interpretation requires context: diet, exercise, medical history, concurrent medications, and other biomarkers. Healthi Life in Ekkamai, Bangkok measures up to 300 biomarkers, reviews them one-to-one with a physician, and builds a personal protocol supervised over months. Your lipid panel is not a report; it is the beginning of a decision.
Every medicine named on this page is dispensed only after a medical consultation at Healthi Life and on a physician's prescription. No dosing schedule is published here; the dose is set by the prescribing physician. This page is published for transparency, not as an offer to supply.
